Locations:


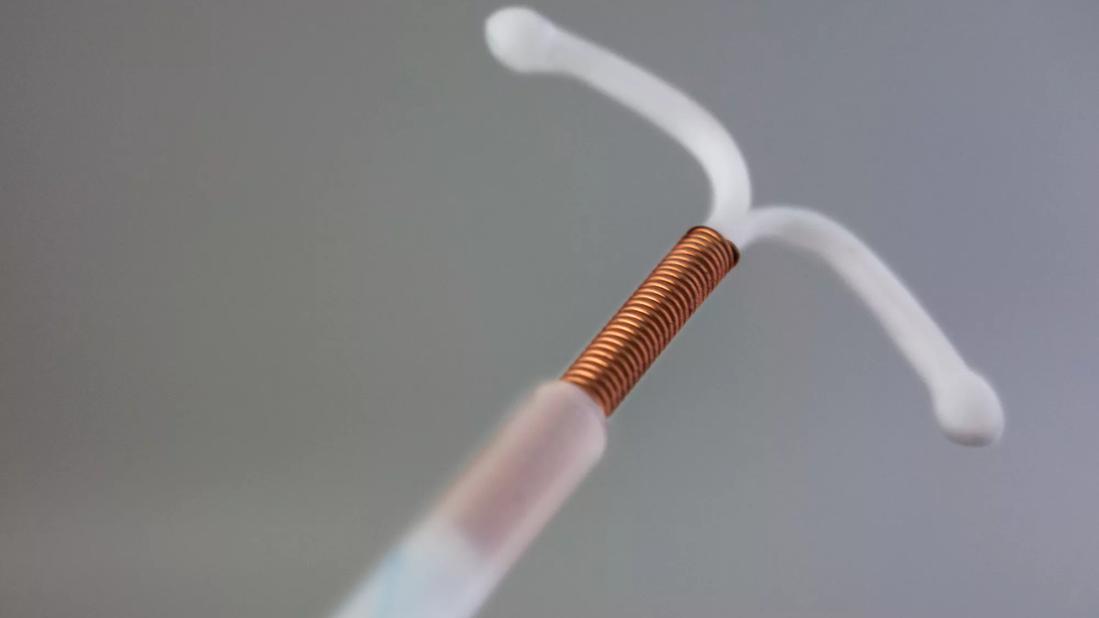
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/160b81be-6189-4308-a777-33648577b09e/IUD-scaled-jpg)
IUD
When Ellen Rome, MD, MPH, and fellow North American Society for Pediatric and Adolescent Gynecology committee members met a few years ago, they committed to leading projects that “changed the temperature of the ocean.”
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
After three years of visiting centers, conducting research, and synthesizing best practices, Dr. Rome and colleagues present a comprehensive toolkit for building and implementing long-acting reversible contraceptive (LARC) programs for adolescents and young adults in primary care and pediatric settings.
When we talked about access to long-acting reversible contraceptives, known as LARCs, and their implementation into primary care and subspecialty practices, we saw plenty of barriers — philosophical and logistical — and not many elegant solutions.
Elegant meaning affordable, easy for the adolescent, easy for the family, easy for the billing and the scheduling teams, etc. And we started asking ourselves, “How do we change this?”
With support from Organon & Co., we spent two years conducting surveys from 17 adolescent medicine and pediatric and adolescent gynecology centers of excellence around the country. We picked the brains of everyone from clinicians and business managers to front desk personnel, and we began to identify and streamline best practices.
Instead of making a paper document that would become obsolete in six months, we created a living document that can evolve and change along with best practices in the field. Here we present a digital toolkit for scaling up the delivery of adolescent-centric counseling within primary care practices for pediatricians and pediatric and adolescent gynecology experts.
Though we started this project several years ago, preventing unplanned pregnancies is perhaps more important today than ever. In a post-Roe world, with many states outlawing access to abortion — often before a person even realizes they’ve missed a period — an unplanned teenage pregnancy can be a family catastrophe.
Advertisement
As healthcare providers, we want positive outcomes no matter who and what and where and how, and we want to have tough conversations in a way that’s patient-positive and family-positive.
We want to meet young people where they are on their reproductive journey in a way that is part of their positive youth development. We also want preventive interventions with respect to unplanned or unintended teen pregnancy, menstrual problem-fixing, and all of the nonreproductive health benefits that reproductive health counseling can facilitate.
Keep in mind, LARCs are also an effective modality for noncontraceptive purposes. Parents are often unaware of the menstrual manipulation that we can do to improve the quality of their child’s life.
For example, patients with catamenial epilepsy may have worsening seizures or loss of bladder and bowel control during certain times of menstruation. In people with developmental disabilities, menstruation can present a major hygiene challenge. Young people with severe dysmenorrhea, menstrual cramps that interfere with life, school and activities, and those with menstrual migraines may experience drastic improvement in their day-to-day life with improved menstrual management.
There are many other clinical scenarios where we can help improve a young person’s quality of life simply by addressing what happens with their periods.
Having tools in your toolkit to make the delivery of appropriate adolescent-centric care easier, accessible, affordable and practical is imperative.
Advertisement
We heard from many colleagues while developing this toolkit. It’s on our primary care clinicians’ minds that we can do better, and it’s relevant for pediatric specialists as well—here’s an example:
When a pediatric cardiologist has a patient after heart transplant with menorrhagia, meaning heavy or prolonged menstrual bleeding, symptoms cannot be managed with a regular birth control bill because of estrogen contraindications. In this case, a LARC may be the best option, but they need a consulting team or center to manage this type of intervention.
The ability to provide a “warm handoff,” where a pediatric cardiologist or pediatrician engages with an adolescent medicine physician, can expedite treatment for this specific reproductive health need.
This toolkit helps pediatricians and primary care clinicians understand basic reproductive health and adolescent-centric counseling. The Adolescent Medicine team is there to help with complex contraceptive needs that impact young people’s lives.
All young patients — whether they require complex support or have uncomplicated healthcare needs — deserve adequate care and counseling on their reproductive health journey.
The bottom line is, our primary care colleagues have said: “We want to learn. How can we do this better? How can we prevent poor outcomes in youth?”
This toolkit is a place to start. It’s a comprehensive resource for building a meaningful and evidence-based program to address an unmet healthcare need for adolescents and young adults.
Advertisement
About the author: Dr. Rome is the Head of the Center for Adolescent Medicine at Cleveland Clinic Children’s Hospital.
Advertisement
Advertisement
Key takeaways from the newest STS-Pedimacs report

Pediatric Syncope Clinic helps rule out serious disease and guide next steps
Cleveland Clinic findings highlight gains in stability, chest wall contouring and correction

What the discovery means for clinicians and patients
Why preparedness matters right now

Early diagnosis, specialized assessment and high-frequency motor-based therapy can improve outcomes

Transplant centers vary substantially in how they assess, document and follow patients after allogeneic transplantation

Helping pediatricians and families make safer, more individualized activity decisions
 Search