Locations:


Instrument aids natural orifice endoluminal surgery
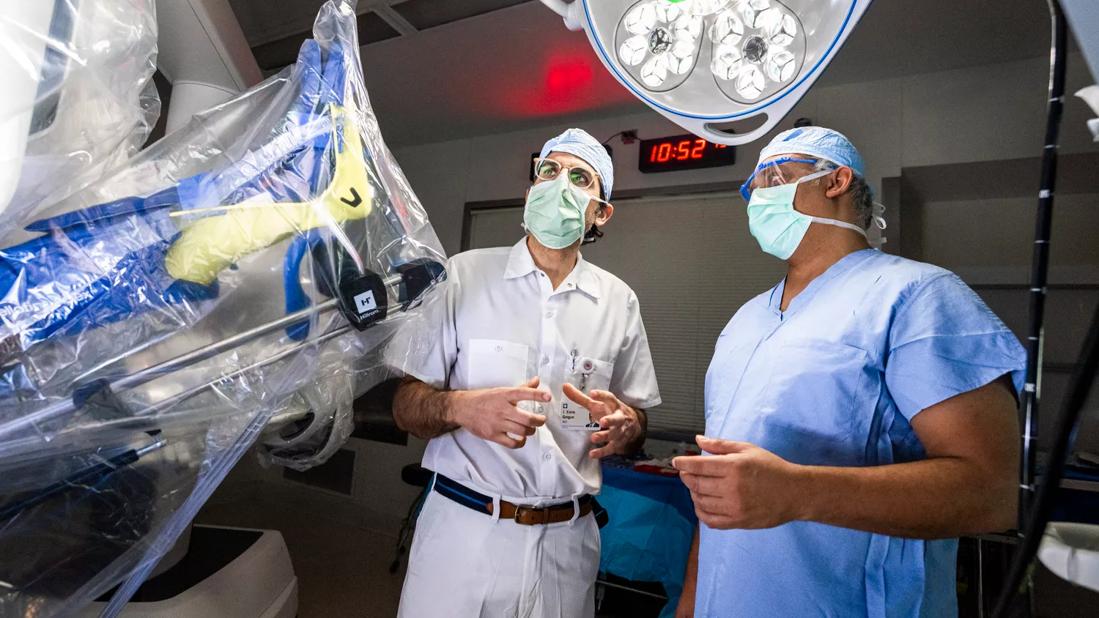
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/0d53d4fa-106f-48ae-b5c2-a2af613e4886/Gorgun-surgery-DDI)
Emre Gorgun, MD
While the excision of premalignant colorectal polyps is necessary to interrupt progression from adenoma to carcinoma, large polyps with complex configurations and/or tortuous locations can be challenging to remove.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Open or laparoscopic colectomy enables the complete excision of polyps that are not amenable to traditional colonoscopic resection, but both procedures entail surgical risk, disrupt bowel function and require an extended hospital stay.
Recently, endoscopic submucosal dissection (ESD) has emerged as a less-invasive option for extracting large, complex polyps. In the hands of a skilled operator, ESD is effective, but the single-channel flexible endoscope has inherent limitations in terms of dexterity, efficiency of instrument use, and achieving adequate traction on the lesion during dissection.
Now, Cleveland Clinic colorectal surgeon Emre Gorgun, MD, has employed a new multi-channel advanced endoscopy instrument to aid endoluminal visualization, retraction and dissection of large, complex polyps. The approach may make ESD less difficult to perform, and help some patients avoid colectomy and preserve bowel.
Dr. Gorgun, who is Director for Lower GI of the Digestive Disease & Surgery Institute’s Endoluminal Surgery Center, has used the DiLumen C2™ device to trans-anally excise complex sigmoid polyps in four patients to date. The initial procedure, performed in August, 2019, marks the first time this specific endoscopic-assist platform was successfully deployed to safely and effectively resect a complex polyp from a patient, according to Lumendi LLC, which developed DiLumen C2 in collaboration with NewYork-Presbyterian/Weill Cornell Medical Center.
“There are challenges to this type of procedure, but the device did what it was supposed to do,” Dr. Gorgun says. “Our Endoluminal Surgery Center is committed to pushing the envelope in terms of organ-sparing and minimally invasive interventions for the gastrointestinal tract. The concept of natural orifice transluminal endoscopic surgery, or NOTES, has been around for a while, but the technology wasn’t there to support it. This is true NOTES; it’s happening here.”
Advertisement
Complex colorectal polyps generally are defined as those greater than 2 cm in diameter. In addition to large size, location in a difficult-to-access area, such as within a diverticula or atop a haustral fold, adds to the challenge of en bloc polyp resection.
The single-channel colonoscope that Dr. Gorgun previously has used for en bloc ESD of complex polyps requires that instruments be used sequentially rather than simultaneously, as would be the case in laparoscopic surgery. First, a catheter is fed through the scope to inject saline in the submucosa beneath the lesion to raise its profile. The catheter is withdrawn and a knife inserted to make a circumferential incision. The scope’s blunt tip is used to lift, manipulate and separate the polyp, an action known as the rhinoceros maneuver. Then, a grasping tool holds the lesion while the scope is retracted.
“Open surgery or laparoscopy allows you to work with two hands,” Dr. Gorgun says. “With flexible endoscopy, you lose that ability.” Even with his extensive ESD experience — having trained in Japan, where the technique originated, and having performed more than 500 procedures since 2011 — “it’s still a single-handed, difficult procedure,” he says.
The DiLumen C2 platform, approved by the Food and Drug Administration in 2018, blends elements of laparoscopy and flexible endoscopy. Dual inflatable balloons extend ahead of and behind the endoscope’s tip to stabilize the shaft, creating a therapeutic “work zone” that helps polyp visualization. In addition to the main endoscope working channel, two 6 mm instrument channels on either side of the shaft accommodate an articulated scissor and grasping tool that can be operated simultaneously to improve retraction while cutting tissue.
Advertisement
Dr. Gorgun had tested an earlier DiLumen model that lacked the outer instrument channels; his feedback contributed to the upgraded device.
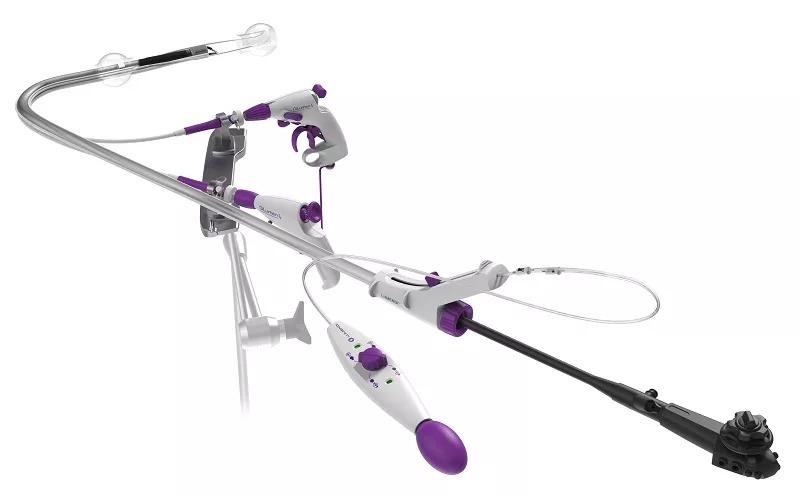
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/bf459c3e-efdd-4b99-b5f2-019e511a69f3/19-DDI-5512-Endoluminal-surgery-device-inset-800-x-450_jpg)
The DiLumen C2 multi-channel advanced endoscopy platform for resection of complex colorectal polyps.
Image courtesy of Lumendi LLC.
In Dr. Gorgun’s initial case using the DiLumen C2, a 72-year-old patient presented with a large, complex polyp in the distal sigmoid, 18 cm from the anal verge. The 4.5 cm lesion was exophytic, fungating and nongranular, with a flat component. Its size and location at a bend in the colon would have made for a challenging ESD with the standard colonoscope.
“With an advanced skill level, this would have been possible to remove, but the C2 platform facilitated the process,” Dr. Gorgun says.
The trans-anal endoluminal procedure took 52 minutes. The patient was discharged the same day. Tissue pathology showed negative margins so laparoscopic colectomy was unnecessary.
With additional experience, Dr. Gorgun says the DiLumen C2 platform could be used to remove early cancerous colorectal polyps as long as they are superficial, as well as to resect other submucosal lesions such as leiomyomas and leiomyosarcomas. Resections higher in the colon, possibly as far as the cecum may also be possible; upper gastrointestinal tract lesions accessed trans-esophageally are potentially feasible, too.
“We need to increase our skills and learn more about the device,” Dr. Gorgun says. “This is a process and an evolution. We need to invest our time and efforts to develop and improve our abilities and technologies, so that we can perform more complex interventions endoluminally.”
Advertisement
Feature image: On the DiLumen C2 instrument, inflatable balloons ahead of and behind the endoscope’s tip aid polyp visualization, while two instrument channels on either side of the shaft accommodate an articulated scissor and grasping tool. Image courtesy of Lumendi LLC.
Advertisement
Advertisement

Adding 177Lu-PSMA-617 to ADT plus an ARPI cut the risk of radiographic progression or mortality by 28%

New program will help patients improve fitness and manage weight after cancer treatment

Cleveland Clinic hematologist highlights new guidelines and treatment advances in immune thrombocytopenia

NIMBLE replaces weekly tumor board delays with same-day multidisciplinary recommendations

Cleveland Clinic study provides validation for the test, which combines AI and pathological data to predict outcomes in postoperative patients

Advanced imaging technology catches metastases much earlier, allowing treatment with fewer side effects

Reduced radiation for lymph node areas reduces side effects

Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
 Search