Locations:


Too far or not far enough? And what implementation means for your patients
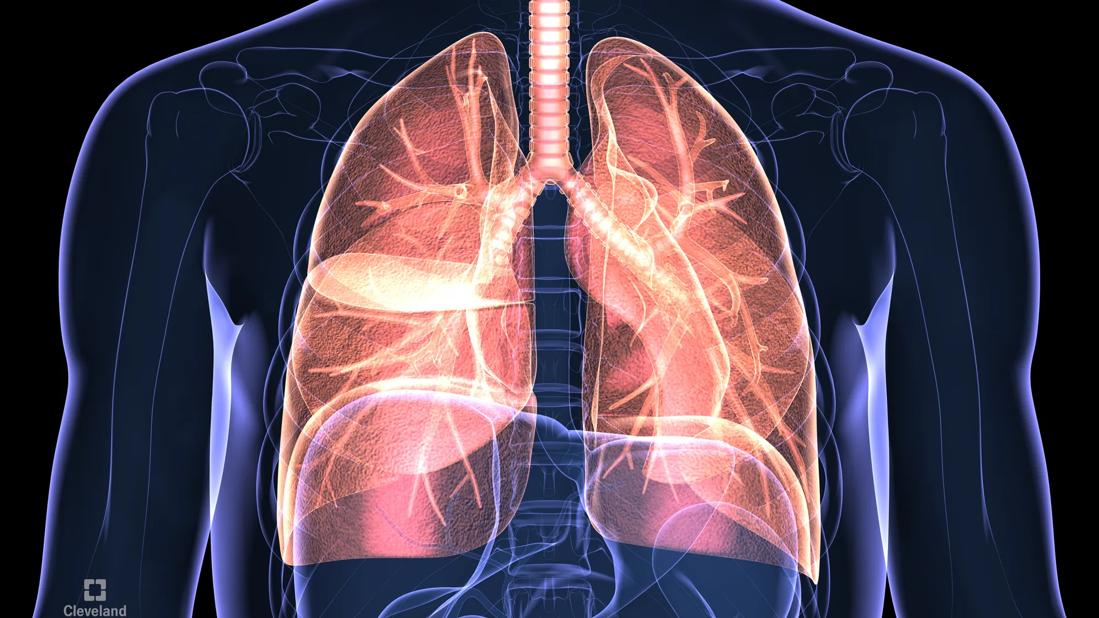
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/eec7f513-0ead-481a-a4d9-a8e99a366db3/lungs-in-chest-83535-jpg)
Lungs
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Individuals who currently or previously smoked (those who have quit in the last 15 years) age 50 to 80 with a 20 pack-year smoking history are now candidates for an annual lung cancer screening. This is according to new recommendations published by the U.S. Preventive Services Task Force (USPSTF).
This change follows new evidence that supports the benefit of screening and better overall management associated with its potential risk. Some estimates suggest this expanded eligibility will increase the screening pool by 80% to 90%.
This new recommendation was supported by USPSTF-initiated modeling studies, in addition to findings from the NELSON trial, a large published study that included a starting age of 50 for trial participants.
However, there is still some debate within the field as to whether or not the recommendations go too far — or not far enough. The camp supporting the latter argument says that individuals who previously smoked and who are ineligible for screening because of the 15-year cut-off still have a relatively high risk of developing cancer. They suggest that targeted screening tools, like risk calculators, could play a vital role in identifying those who do not meet the new recommendations but may still benefit from screening. On the other hand, others argue that more restrictive criteria are beneficial, sifting out low-risk candidates and, thus, reducing screening exposures, including unnecessary biopsy of (most commonly) benign lung nodules, radiation exposure and undue anxiety.
Advertisement
It’s an important and well-intentioned debate ultimately derived from a desire to improve patient outcomes. It’s also important to remember that lung cancer screening is more complex than the selection criteria alone. A robust screening program means developing outreach and education initiatives, thorough and collaborative diagnostic management and tracking, and smoking cessation and other support programs. Regardless of your views on screening parameters, there is a consensus that high-quality lung cancer screening is paramount. More specifically, this means an investment in the following:
Operationalizing these changes may still take time. Private insurers can change their coverage rules anytime between now and the end of 2022. The Centers for Medicare & Medicaid Services will take up a new net coverage determination with a decision expected in 9 to 12 months. Importantly, because many insurers are making coverage changes now, clinicians need to be aware of the criteria and refer those with coverage for screening.
Advertisement
We look forward to a time when the majority of lung cancers are screen-detected. The updated USPSTF recommendations are a step in that direction.
About the author: Dr. Mazzone is Director of the Lung Cancer Program and Lung Cancer Screening Program for the Respiratory Institute.
Advertisement
Advertisement

CELMoD therapy receives approval based primarily on measurable residual disease

Are we missing patients?

Expanding treatment options for patients with advanced and recurrent rectal cancer

Study analyzes creative approaches to support people facing housing insecurity
Evaluating AI initiatives and their impact on operations and care delivery

Study reinforces the importance of genetic testing prior to local therapy decisions

Understanding expanding treatment options and potential advances
Adding 177Lu-PSMA-617 to ADT plus an ARPI cut the risk of radiographic progression or mortality by 28%
 Search