Locations:


Condition is characterized by left heart defects
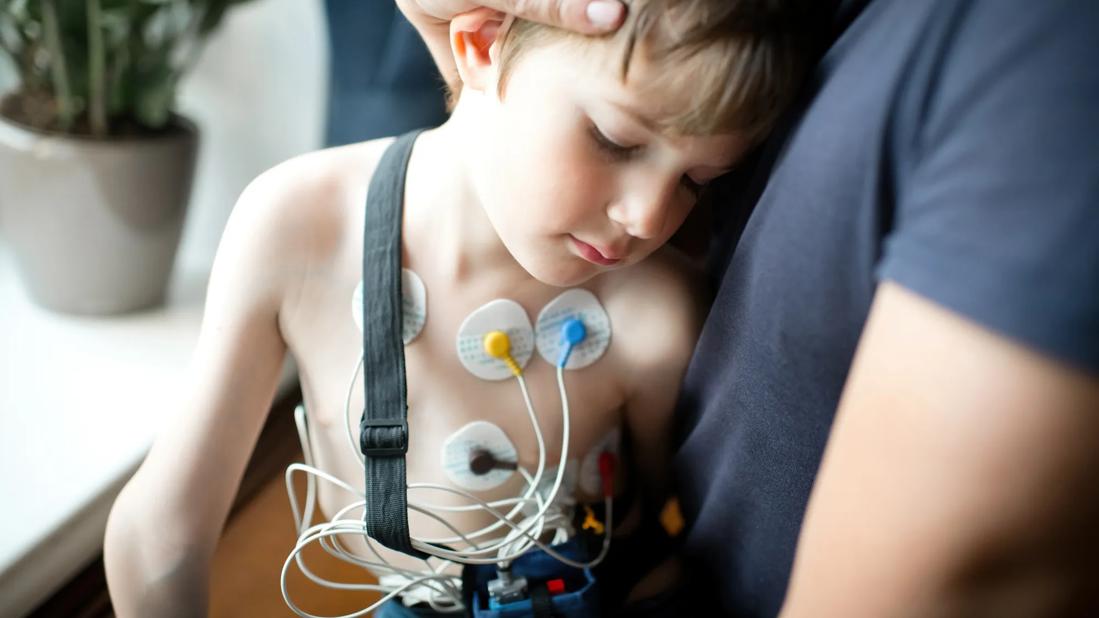
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/e4c100c3-7db9-467a-b8f1-f44b057f6182/child-ekg-1502466766)
Child undergoing an ECG
Shone’s complex (or syndrome) is a rare congenital heart condition characterized by multiple left heart defects. It accounts for approximately 0.6 percent of all cases of congenital heart disease. Due to a wide array of potential left heart manifestations that may include coarctation of the aorta, subaortic stenosis, supravalve mitral membrane and parachute mitral valve, the outcomes of patients with Shone’s complex can vary.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
“The prognosis for this condition is difficult to predict, but how well a patient will do ultimately depends on how big the left ventricle and left side of the heart is,” explains Holly Nadorlik, DO, Pediatric Cardiologist at Cleveland Clinic Children’s. “Those patients who present with a coarctation of the aorta often require surgery. Occasionally, patients also need additional interventions such as valve repairs or replacements, or subaortic membrane resections.”
Dr. Nadorlik recently provided prenatal cardiology care for a baby from Cleveland who presented with Shone’s complex at the gestational age of 18 weeks.
“A routine ultrasound at 18 weeks revealed that the baby had a smaller left side of the heart than right side, with smaller valves on the left side of the heart, which raised suspicion of Shone’s complex,” she says. “Because it can be really difficult to predict if the left side of the heart will continue to grow, we continued to monitor her with regular monthly ultrasounds until delivery.”
High-risk babies are delivered in Cleveland Clinic’s Special Delivery Unit (SDU) where different types of specialty care can be provided to pediatric patients. When delivery time came around for Dr. Nadorlik’s patient, a team of healthcare providers, including an obstetrician, pediatric interventional cardiologist and a pediatric cardiac intensive care doctor, was ready to intervene.
“After delivery, the atrial septum was noted to be restrictive which, combined with a small left heart, made the baby unstable,” says Dr. Nadorlik.
Advertisement
The patient was transferred to the catheterization laboratory right after delivery where the atrial septum was dilated using balloon angioplasty.
“This procedure allowed decompression of the left atrium, which was needed due to the small left heart,” explains Dr. Nadorlik.
Although the initial intervention went well, a few days after the delivery another operation to repair coarctation of the aorta and widen the aortic arch was needed. Hani Najm, MD, Chair of Pediatric and Congenital Heart Surgery at Cleveland Clinic, performed the procedure.
“The baby did very well after the surgery and remained in the hospital for 25 days,” says Dr. Nadorlik. “Following, she was discharged with a prescription of Lasix® and enalapril and is currently being seen every few months to monitor the mild mitral stenosis and bicuspid aortic valve. These issues are minor and are not affecting her growth and development.”
Dr. Nadorlik emphasizes that “planning for delivery and anticipating potential issues in patients with Shone’s complex is really important, as is delivery at a tertiary center with access to surgery and the catheterization laboratory, if needed.”
Adequate prenatal care, careful delivery preparation, and a team approach to care, maximize the chances of a positive outcome in Shone’s complex cases.
“Preparing for delivery and anticipating issues that may occur after [the delivery] allowed us to give the best care to the patient. She is doing well now and is an active toddler – really, the best outcome we could have hoped for,” concludes Dr. Nadorlik.
Advertisement
Advertisement
Key takeaways from the newest STS-Pedimacs report

Pediatric Syncope Clinic helps rule out serious disease and guide next steps
Cleveland Clinic findings highlight gains in stability, chest wall contouring and correction

What the discovery means for clinicians and patients
Why preparedness matters right now

Early diagnosis, specialized assessment and high-frequency motor-based therapy can improve outcomes

Transplant centers vary substantially in how they assess, document and follow patients after allogeneic transplantation

Helping pediatricians and families make safer, more individualized activity decisions
 Search