Locations:


Prompt treatment can improve outcomes
Podcast content: This podcast is available to listen to online.
Listen to podcast online (https://www.buzzsprout.com/2243576/13534550)
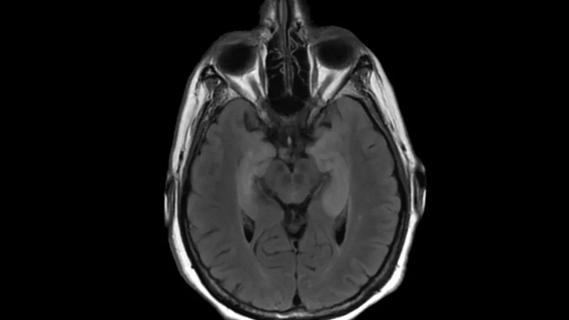
The field of autoimmune neurology is rapidly gaining recognition, particularly in regard to patients with status epilepticus and sudden severe neurocognitive or neuropsychiatric changes. However, autoimmune causes often are overlooked in patients with more subtle abnormalities — such as mild to moderate cognitive changes, seizure auras and faciobrachial seizures, says Amy Kunchok, MD, a neurologist who specializes in the field at Cleveland Clinic.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
In the newest episode of Cleveland Clinic’s Neuro Pathways podcast, Dr. Kunchok explains more about this nascent subspecialty. She briefly discusses:
Click the podcast player above to listen to the episode now, or read on for a short edited excerpt. Check out more Neuro Pathways episodes at clevelandclinic.org/neuropodcast or wherever you get your podcasts.
Podcast host Glen Stevens, DO, PhD: Monthly you’ve been running a very interesting neuroimmunology encephalitis conference where we’ve discussed cases on service. There was an interesting case of faciobrachial seizures recently. Can you talk about that disorder a bit?
Dr. Kunchok: We recently discussed anti-LGI1 encephalitis in our case conference, and we talked about faciobrachial dystonic seizures and the clinical presentation — how these seizures may involve even just subtle movements of the hand or arm. These can be dystonic-like movements. They also can involve facial movements. These movements are often subtle at the beginning and can have normal EEG, without an epileptic correlate in some of these cases, which can make it difficult to recognize them. But this is a very pathognomonic finding for anti-LGI1 encephalitis.
Advertisement
A less common phenotype was seen recently in some of our patients with pilomotor seizures, where they basically have goosebumps. One patient we discussed had some bradycardiac episodes as well, which is an interesting phenotype that is less common but also described in anti-LGI1 encephalitis.
**********************************************************************************
Among our current cohort of patients, there are quite a few who have anti-LGI1 encephalitiswho have done very well with steroids. Some of them have additional immunotherapy — for example, rituximab — but they’ve done very well and have improved in their cognition. The faciobrachial dystonic seizures have settled down with immunotherapy, and some patients have even returned to work. I have one patient who returned to work within three months of receiving immunotherapy.
Additionally, with anti-NMDA-R encephalitis — which in some cases can be a severe encephalitis — we have had quite a few patients who have been treated very promptly within the hospital service. Their seizures have settled down, and within a year several young patients returned to study or work. Actually, we have one patient who’s completing a degree at present, only one year after having anti-NMDA-R encephalitis. So there have been some very good outcomes as a result of prompt immunotherapy in the acute setting, probably in addition to some longer-term immunotherapy.
Advertisement
Advertisement

Housing multidisciplinary clinicians in one leading-edge facility can transform GME along with patient care
How ongoing efforts will be bolstered by Cleveland Clinic’s new Neurological Institute building
Foundation model reveals latent risk structures in sleep physiology that elude conventional metrics

Where the field is moving and what Cleveland Clinic has in the works
Expanded bevy of dedicated ORs will feature customized designs, leading-edge technology, optimized workflows
Research could lead to bionic devices that work more like the human body

Multicenter study offers guidance on when to consider extended monitoring
Findings may have implications for understanding the disorders’ pathophysiology
 Search