Locations:


Overall survival benefit not established
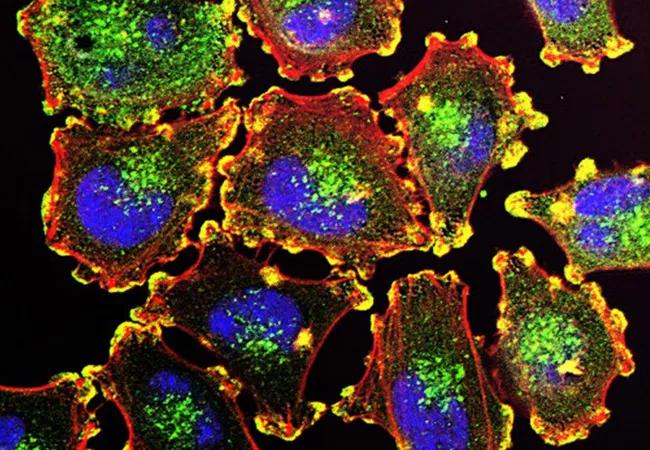
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/a6e31f9f-01ab-41dc-a35e-c001e5f3ecc9/nci-vol-9872-72_650x450_jpg)
Metastatic melanoma cells. Image source: National Cancer Institute
The immune checkpoint inhibitor and anti-PD-L1 monoclonal antibody pembrolizumab improves relapse-free survival (RFS) but not overall survival (OS) when compared with other adjuvant treatments for patients with high-risk resected melanoma, according to the final analysis of the SWOG S1401 phase 3 randomized trial. Researchers presented the analysis at the American Society of Clinical Oncology’s 2021 annual meeting.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Two FDA-approved adjuvant therapies are available to patients with advanced high-risk resected melanoma — high-dose interferon and high-dose ipilimumab — but their therapeutic index is modest given the high toxicity of the treatments. “The S1404 study has been looking at pembrolizumab as a potential adjuvant option for these patients because it has low toxicity overall and a good response rate in patients with stage IV disease,” notes Pauline Funchain, MD, staff in the Department of Hematology and Medical Oncology at Cleveland Clinic Cancer Center and coauthor of the study. “This analysis confirms that pembrolizumab can help patients stay disease free for longer.”
Adult patients with stages IIIA(N2), IIIB, IIIC and IV (M1a, b, c) but without brain metastases were eligible. All patients who entered the study had surgically resected melanoma, including lymph node dissection for positive disease, as well as no prior exposure to PD-L1 blockade, ipilimumab or interferon.
Patients were enrolled between 2015 and 2017 and separated into two treatment arms based on stage, PD-L1 staining status and intended control arm. Patients were randomized 1:1 to the control arm or experimental arm. The control arm treatment included interferon alfa-2p 20MU/m2 IV days 1-5, weeks 1-4, followed by 10 MU/m2/d SC days 1, 3 and 5, weeks 5-52 (N = 190) or ipilimumab 10 mg/kg IV every three weeks for four doses, then every 12 weeks for up to three years (N = 465). Patients in the experimental arm received pembrolizumab 200 mg IV every three weeks for a year (N = 648).
Advertisement
Researchers focused on three primary comparisons in the per-protocol final analysis: RFS and OS among all patients, as well as OS among patients with PD-L1 positive status. Of the 1,345 patients randomized, 11% had AJCC7 stage IIA(N2), 49% were IIIB, 34% were IIIC and 6% were stage IV.
The pembrolizumab group experienced a significant improvement in RFS compared with the control group (HR 0.740, 99.618% CI, 0.571 to 0.958). Neither the patients with PD-L1 positive baseline biopsies nor the overall patient population experienced a significant improvement in OS (HR 0.847, 96.3% CI, 0.622 to 1.297), and HR 0.883, 97.8% CI, 0.604 to 1.291), respectively. Patients in the pembrolizumab arm experienced significantly fewer grade 3 adverse events than patients in the control arm.
The lack of OS benefit of adjuvant pembrolizumab raises questions about treatment timing for patients with high-risk resected melanoma.
“The data on relapse-free survival and toxicity are encouraging. Every additional scan that is free of disease is a big deal for a patient,” says Dr. Funchain. “On the other hand, these data provide some reassurance for patients who may be hesitant for personal or medical reasons to take on adjuvant immunotherapy. At least in in the short term, we see little to no detriment in terms of survival. But the findings regarding overall survival truly need longer follow up in order to fully understand the long-term benefits of adjuvant therapy.”
Advertisement
Advertisement
NIMBLE replaces weekly tumor board delays with same-day multidisciplinary recommendations
Cleveland Clinic study provides validation for the test, which combines AI and pathological data to predict outcomes in postoperative patients
Advanced imaging technology catches metastases much earlier, allowing treatment with fewer side effects
Reduced radiation for lymph node areas reduces side effects
Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
This single-port option offers advantages for appropriate patients

Practice changes needed to expand access across academic and community settings
Treatment yields positive results despite late diagnosis and cardiac involvement
 Search