Locations:


Better assessing individual risk of recurrence
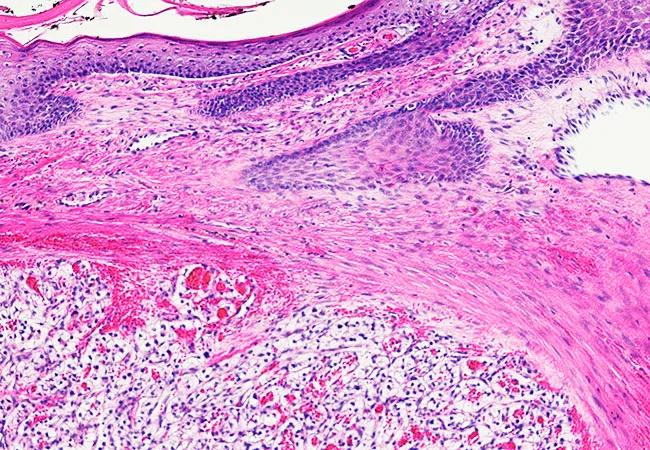
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/4acd9ec1-8d24-4eee-82cf-cf4a26b8c270/650x450-renal-cell-carcinoma_jpg)
650×450-renal-cell-carcinoma
Among patients with clinically localized renal cell carcinoma (RCC), 30% will relapse with distant metastatic disease after nephrectomy. The risk of recurrence influences the intensity of follow-up imaging, the guidance provided to patients, and consideration of adjuvant treatment and clinical trials.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Predicting recurrence can be challenging: The commonly used prognostic models, such as SSIGN and UISS, consider only clinicopathologic variables such as T stage and grade and do not capture tumor biology or adequately discriminate recurrence risk. They are also subject to varied interpretations by observers.
Over the past decade, multigene assays have been developed for RCC that provide information beyond traditional parameters in multiple tumor types that can better assess individual risk. At the 2019 Genitourinary Cancers Symposium, Brian Rini, MD, leader of Cleveland Clinic’s Genitourinary Program, provided an overview of genetic prognostic models for RCC.
A multigene signature based on cell cycle proliferation (CCP) was developed based on 565 patients at Massachusetts General Hospital and the University of Michigan who underwent radical nephrectomy for localized phase T1-T3 clear cell, papillary or chromophobe RCC.
RNA was extracted from the highest grade area of the viable tumor, and CCP score was calculated based on the unweighted average of 31 cell cycle genes normalized to the expression of 15 housekeeping genes. The CCP score was compared with the Karakiewicz nomogram, and a composite (R-CCP) score was developed.
The CCP score was an independent predictor of recurrence (hazard ratio [HR] 1.50, 95% confidence interval [CI], 1.07-2.09) and disease-specific mortality (HR 2.49, 95% CI, 1.53-4.04). Combining the molecular classifier with baseline clinical variables allowed for accurate, patient-specific risk assessment to guide clinical management.
Advertisement
ClearCode34, a 34-gene classifier for assigning tumors to good risk (ccA) and poor risk (ccB) subtypes, was based on 72 clear cell RCC sample standards. The classifier was applied to RNA-sequencing data from 380 nonmetastatic clear cell RCC samples from The Cancer Genome Atlas and 157 clinical samples collected at the University of North Carolina.
The ccA tumors overexpressed genes associated with hypoxia, angiogenesis, fatty acid metabolism and organic acid metabolism. The ccB tumors overexpressed genes that regulate epithelial to mesenchymal transition, the cell cycle and wound healing.
ClearCode34 had a hazard ratio for disease-specific mortality of 2.9. This model provides prognostic stratification that improved upon established algorithms to assess risk for recurrence and death for nonmetastatic clear cell RCC patients.
In developing this assay, 732 genes from published data and biologic pathways that are functionally important in clear cell RCC were analyzed for their association with clinical outcomes in 942 Cleveland Clinic patients with stage I-III clear cell RCC who had undergone a nephrectomy. A total of 516 genes were associated with recurrence-free interval, and 11 were selected by further statistical analyses and combined with five reference genes to develop a recurrence score algorithm.
The 16-gene recurrence score was initially validated in an independent cohort of 626 patients with stage I-III clear cell RCC who had also undergone nephrectomy. In multivariate analyses, the recurrence score was significantly associated with the risk of tumor recurrence (HR per 25-unit increase in the score 3.37 [95% CI, 2.23-5.08]). It was able to identify a clinically significant number of both high-risk stage I and low-risk stage II-III patients.
Advertisement
In a second validation study, the 16-gene assay was evaluated in 212 patients, with a focus on 193 with stage III RCC, from the S-TRAC randomized trial of adjuvant sunitinib. The 16-gene recurrence score results predicted time to recurrence, disease-free survival and renal cancer-specific survival in both arms, with the strongest results observed in the placebo arm. When high versus low recurrence score groups were compared, the HR for recurrence was 9.18 (95% CI, 2.15-39.24) in the placebo arm. The study provided 1B evidence for the 16-gene assay, offering the strongest evidence base of the three genetic models.
Genetic models have the potential to refine the risk of recurrence and guide physician management and physician and patient decisions concerning adjuvant treatment. As yet, they have not been used in clinical settings. Based on the evidence to date, Dr. Rini recommends further investigation of genetic models for predictive value, utility in adjuvant IO trials and other settings, such as SRM.
Advertisement
Advertisement

Adding 177Lu-PSMA-617 to ADT plus an ARPI cut the risk of radiographic progression or mortality by 28%

New program will help patients improve fitness and manage weight after cancer treatment

Cleveland Clinic hematologist highlights new guidelines and treatment advances in immune thrombocytopenia

NIMBLE replaces weekly tumor board delays with same-day multidisciplinary recommendations

Cleveland Clinic study provides validation for the test, which combines AI and pathological data to predict outcomes in postoperative patients

Advanced imaging technology catches metastases much earlier, allowing treatment with fewer side effects

Reduced radiation for lymph node areas reduces side effects

Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
 Search