Locations:


Emerging technology can quantify multiple properties of brain tissue in a single scan
Podcast content: This podcast is available to listen to online.
Listen to podcast online (https://www.buzzsprout.com/2243576/13534557)
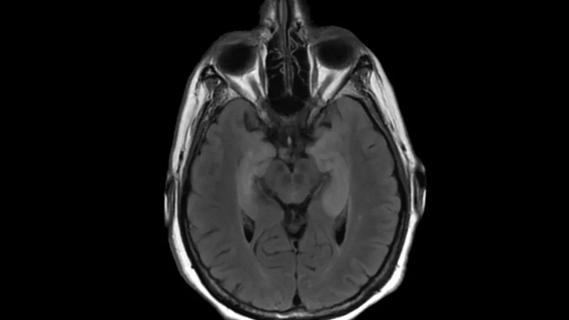
Magnetic resonance (MR) fingerprinting is more about data than imaging. The novel technology uses conventional MRI scanners but can quantify multiple properties of tissue in a single scan, characterizing areas smaller than a single voxel in a fraction of the time. Full brain imaging now can be done in three to five minutes.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
The benefits of MR fingerprinting could improve how neurological specialists identify lesions in epilepsy, evaluate microstructures of the brain in multiple sclerosis and even detect neurodegenerative disease.
The newest episode of Cleveland Clinic’s Neuro Pathways podcast reviews the latest on this emerging form of brain imaging. Neurologist Daniel Ontaneda, MD, PhD, and epilepsy researcher Irene Wang, PhD, discuss:
Click the podcast player above to listen to the episode now, or read on for a short edited excerpt. Check out more Neuro Pathways episodes at clevelandclinic.org/neuropodcast or wherever you get your podcasts.
Dr. Ontaneda: MRI is a time-tested method that we use in multiple sclerosis (MS) both to make a diagnosis and to follow treatment response. We do this mainly by identification of white matter lesions in the brain and spinal cord. But we’ve known for years that despite how useful MRI is in MS, there is something called a clinico-radiological paradox. That is, some patients have MRIs that don’t look that bad, but clinically they’re not doing well at all. And we have other patients whose MRIs look terrible, with a lot of lesions, and you would expect them not to be well clinically, but they’re actually doing OK.
We also know, based on pathological studies, several done at Cleveland Clinic, that there’s a lot of heterogeneity between one MS plaque and another. About 30% of lesions that we find on MRI in MS actually aren’t even demyelinated. We published a couple of years ago that about 10% of patients from our postmortem program had no cerebral demyelination whatsoever, but their MRIs looked like MS. This leads us to conclude that while MRI is sensitive for diagnosis of MS and sensitive to demyelination, perhaps it’s not specific.
Advertisement
MS also has a neurodegenerative component. There is a process that, working slowly over time, makes the brain shrink.
So, we have adapted the use of MR fingerprinting specifically to answer questions related to these issues. We’ve done two studies. One was conducted among 55 subjects. Some of them had MS. Some of them were controls. We tried to find a fingerprint or a signature that let us diagnose MS based on what the MRI data was showing. Indeed, we found that there were significant differences in healthy controls, early MS patients and later MS patients.
We reproduced that data in a second study, where we focused on a deep structure in the brain called the thalamus…. We know that the thalamus is one of the areas that changes earliest in MS. It actually starts shrinking, and we know that it contains both white matter and gray matter. It has lesions (plaques) in it as well as non-lesional pathology.
So, we thought the thalamus was probably the best place to use a sequence like MR fingerprinting to study the microstructure of that organ and see what was actually changing. What we found was quite interesting: The thalamus was changing, not because of changes in the relaxation values in the thalamus itself, but because of changes in the relaxation values in the white matter outside the thalamus. It was somewhat surprising. Instead of thinking of the thalamus as a generator of neurodegeneration, it’s more of a barometer of neurodegeneration.
Dr. Wang: I’ll give you a couple of examples that may highlight the additional value of MR fingerprinting in epilepsy. The first example is periventricular nodular heterotopia, a type of cortical malformation frequently associated with medically intractable seizures. This type of malformation usually presents with multiple nodules along the ventricles, sometimes bilateral. On a clinical MRI scan, the lesions appear to have the same signal intensity, so you’re not able to distinguish one from another. We have reported a very interesting case where, with MR fingerprinting, some nodules were significantly different from the rest. But was this relevant to the epilepsy? After invasive evaluation with intracranial EEG, the nodules with distinct signal differences were indeed confirmed to cause the patient’s epilepsy. Surgical resection of these nodules gave the patient seizure freedom. This is a great example showing the improved characterization of epileptic lesions.
Advertisement
Another example is on lesion detection for subtle focal cortical dysplasia. This is another critical malformation very frequently associated with epilepsy. Some of these lesions are so small, so subtle, that they are missed in the reading of clinical MRI. We have reported an intriguing case where MR fingerprinting visualized additional tissue alterations at the depth of sulcus. We saw that EEG monitoring results were consistent with the location of the abnormality. Surgery completely removed the abnormality, and the patient became seizure-free. Surgical pathology also confirmed the abnormality.
Advertisement
Advertisement

Housing multidisciplinary clinicians in one leading-edge facility can transform GME along with patient care
How ongoing efforts will be bolstered by Cleveland Clinic’s new Neurological Institute building
Foundation model reveals latent risk structures in sleep physiology that elude conventional metrics

Where the field is moving and what Cleveland Clinic has in the works
Expanded bevy of dedicated ORs will feature customized designs, leading-edge technology, optimized workflows
Research could lead to bionic devices that work more like the human body

Multicenter study offers guidance on when to consider extended monitoring
Findings may have implications for understanding the disorders’ pathophysiology
 Search