Locations:


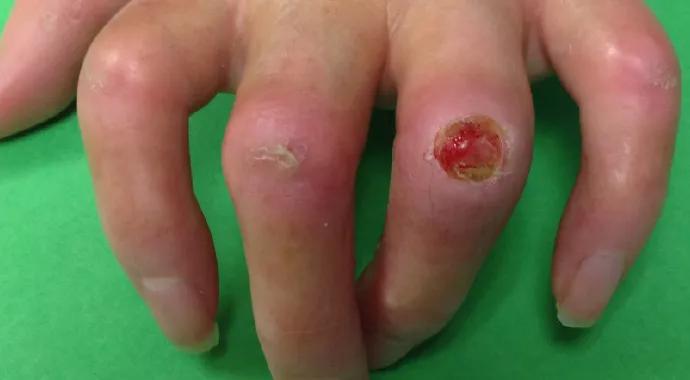
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/6e623fdb-ec14-40c8-affb-387d895ab780/15-RHE-1651-Chatterjee-Hero-Image-690x380pxl_jpg)
15-RHE-1651-Chatterjee-Hero-Image-690x380pxl
By Soumya Chatterjee, MD, MS, and Pichaya OCharoen, MD
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
The increased incidence of malignancies in systemic sclerosis (SSc) accounts for about 10 percent of the mortality in this disease. In 1979, a study showed that 4 percent of SSc patients developed cancer, most commonly breast cancer, followed by lymphoma/leukemia, gastrointestinal malignancy and cervical cancer. Subsequent studies demonstrated high standardized incidence ratios (SIR) of overall cancer, lung, bladder and liver cancer, and hematologic malignancies.
The three main autoantibodies associated with SSc are anti-centromere, anti-Scl-70, and anti-RNA polymerase III (RNAP III). Prior studies have shown that patients with RNAP III tend to have a close temporal correlation between onset of cancer and that of SSc. Breast cancer was the most common cancer reported in these studies.
RNA polymerase III is involved in protein synthesis and cell growth, and was found to be overexpressed in both metaplastic and neoplastic cells. Nucleolar staining of RNA polymerase III was found exclusively in breast and ovarian cancer tissue from RNAP III-positive SSc patients, but not from RNAP III-negative SSc patients or normal controls. This finding suggests that RNA polymerase III expression in tumor cells might trigger the autoantibody response. Mutations in the POLR3A gene were found in tumors from some patients with positive RNAP III. Mutated RNA polymerase III was shown to generate RNAP III that cross-reacted with wild-type RNA polymerase III. Interestingly, mutated RNA polymerase III also triggered specific T cell response.
Advertisement
Several hypotheses have been proposed to explain the pathogenesis of malignancy in SSc. Malignant transformation could occur secondary to chronic inflammation and fibrosis. For example, lung cancer has been associated with interstitial lung disease. Moreover, immunosuppressive medication use, particularly cyclophosphamide, has been associated with bladder cancer and hematologic malignancies. Although mycophenolate mofetil is increasingly being used in scleroderma patients, its association with development of malignancy is unknown at this time. The close temporal correlation between cancer diagnosis and SSc onset in patients with positive RNAP III raises the possibility that in this autoantibody subset, Ssc may occur as a paraneoplastic phenomenon.
There are conflicting reports of incidence of breast cancer in SSc. Some studies have shown an increased incidence, with SIR ranging between 1.62 and 6.1. Other studies have failed to show this increased incidence. In addition, two studies demonstrated a close temporal correlation between the onset of SSc and breast cancer: 11.5 months and 2.5 years, respectively. However, in other studies, the median interval between onset of breast cancer and that of SSc was more than five years. To clarify these reported controversies, our group became interested in studying the development of breast cancer in SSc patients and comparing them with a nonscleroderma cohort of breast cancer patients.
We conducted a retrospective chart review to analyze the relationship between breast cancer and scleroderma in patients who were seen at Cleveland Clinic between January 2006, and May 2016. We compared 51 SSc patients who developed breast cancer (identified by ICD-9 and ICD-10 codes) with 102 patients with breast cancer alone. We excluded patients with mixed connective tissue disease or scleroderma-myositis overlap.
Advertisement
In our study, all patients were females, and most of them were Caucasian in their late 50s. Most patients had limited cutaneous SSc, with positive anticentromere antibody. This was followed in prevalence by RNAP III and anti-Scl-70 antibody, respectively. About a fifth of patients with positive RNAP III developed SSc within three years of breast cancer diagnosis. We found that the interval of SSc onset at breast cancer diagnosis was much shorter in RNAP III-positive patients compared with anticentromere and anti-Scl70 antibody positive patients. However, this association did not achieve statistical significance, probably because of small sample size.
SSc patients who subsequently developed breast cancer received less radiation therapy compared to patients with breast cancer alone. Also, patients with breast cancer and SSc had much higher mortality compared to patients with breast cancer alone. Further investigations with larger sample sizes are necessary to explore the relationship between SSc and malignancy.
Dr. Chatterjee directs the Scleroderma Program in the Department of Rheumatic and Immunologic Diseases. Dr. OCharoen is a fellow in the department.
Advertisement
Advertisement
Cleveland Clinic study provides validation for the test, which combines AI and pathological data to predict outcomes in postoperative patients
Advanced imaging technology catches metastases much earlier, allowing treatment with fewer side effects
Reduced radiation for lymph node areas reduces side effects
Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
This single-port option offers advantages for appropriate patients

Practice changes needed to expand access across academic and community settings
Treatment yields positive results despite late diagnosis and cardiac involvement

Early detection program integrates multiple disciplines to reduce screening barriers and patient anxiety
 Search