Locations:


Patients with genetic mutation need more than ocular treatment
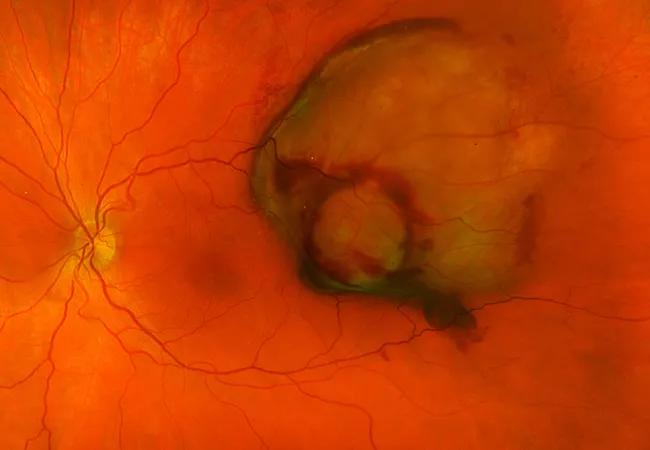
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/0a8eb9ce-321b-41f6-b5a7-da50565daaba/21-EYE-2340059-CQD-Cured-fractions-of-uveal-melanoma_Arun-Singh_jpg)
21-EYE-2340059 CQD Cured fractions of uveal melanoma_Arun Singh
The impact of ocular treatment on the overall survival of people with uveal melanoma has been largely unknown. While some believe that earlier treatment leads to a higher rate of survival, others believe treatment to be equally effective no matter when performed.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
A recent study in JAMA Ophthalmology has shed new light on cure rates in uveal melanoma, presenting a clearer — although not necessarily brighter — view of the lifesaving potential of ocular treatment.
“The overall survival of patients with uveal melanoma has not improved in the last 40-plus years,” says Arun D. Singh, MD, Director of Ophthalmic Oncology at Cleveland Clinic’s Cole Eye Institute. “Now we know why we haven’t seen improvement like we’ve seen in breast, lung, prostate and other cancers: ocular treatment is not curative for the highest-risk forms of uveal melanoma.”
Dr. Singh, lead author of the study, and two cancer biostatisticians Emily C. Zabor, DrPH, and Tomas Radivoyevitch, PhD, calculated the excess absolute risk of mortality in uveal melanoma using Surveillance, Epidemiology, and End Results (SEER) data of more than 10,000 patients diagnosed from 1975 to 2016. They identified three groups of patients, those that:
“There was a spike in deaths at three years and then again at 15 years, and then deaths from uveal melanoma leveled off,” says Dr. Singh.
Curative fraction (the statistical cure rate) was approximately 60% at 25 years.
The team also studied records from nearly 800 patients treated at European medical centers that conducted mutation testing on uveal tumors. They found a correlation between early deaths and BAP1 mutation, and later deaths and SF3B1 mutation. The third group of patients, who did not die from uveal melanoma, did not have these genetic mutations.
Advertisement
“All of these patients had received standard-of-care ocular treatment for uveal melanoma,” says Dr. Singh. “But despite treatment, those who had a mutation died at some point, early or later, and those without a mutation didn’t die of uveal melanoma at all. This may indicate that those who died may have been undertreated and could have benefited from adjuvant therapy.”
These findings raise questions about the survival benefits of current ocular therapy for uveal melanoma and the need for new clinical approaches.
“It’s mutation — more than size, location or any other tumor characteristic — that determines risk of mortality from uveal melanoma,” says Dr. Singh. “We should be looking for mutations at the outset.”
Safe techniques for tumor biopsy should be developed, he adds, to help ophthalmologists identify mutational status, thus determining which patients must be treated and how.
“For patients with genetic mutations, eye treatment by itself is insufficient,” says Dr. Singh. “We need to treat the eye because the tumor can cause blindness, detachment and pain. But for the patient’s survival, we need to do more, such as using adjuvant therapy.”
Today adjuvant therapy for uveal melanoma is uncommon, although multiple clinical studies are in progress.
“For patients with small tumors and no genetic mutations, observation may be the best approach, especially for those who are asymptomatic or more likely to lose vision or experience other adverse effects of treatment,” he says. “No patients with these tumors died of metastatic uveal melanoma. We could even consider discontinuing surveillance after 15 years in patients with good prognoses.”
Advertisement
Advertisement
This single-port option offers advantages for appropriate patients

Practice changes needed to expand access across academic and community settings
Treatment yields positive results despite late diagnosis and cardiac involvement

Early detection program integrates multiple disciplines to reduce screening barriers and patient anxiety
Newer class of medications evolves care models for patients with hemophilia

Improving access to specialists
Dotatate PET/CT scan and molecular testing informed treatment trajectory

A proactive, framework-based approach
 Search