Locations:


New findings could shape the treatment paradigm for a select group of bladder cancer patients
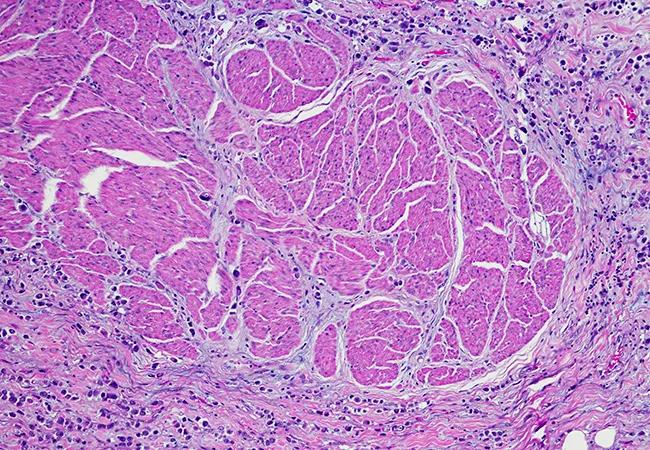
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/0d03a70a-a5df-4a37-98ae-8737f1aede5d/Capture_jpg)
Plasmacytoid variant of urothelial carcinoma
Findings from a new Cleveland Clinic-led study help clarify the role of neoadjuvant chemotherapy in the management of bladder cancer with variant histology. Researchers presented these data at the 2021 American Urological Association meeting.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
The prognosis for variant histology is generally worse than that of pure urothelial carcinoma. The treatment paradigm for the latter includes neoadjuvant chemotherapy with cisplatin followed by radical cystectomy. Treatment for non-muscle invasive bladder cancer with variant histology favors an aggressive therapeutic approach, progressing to radical cystectomy as a first-line therapy and bypassing neoadjuvant treatment altogether.
For patients with muscle-invasive bladder cancer with variant histology (with the exception of small cell carcinoma), the use of neoadjuvant treatment is unclear.
Rebecca Campbell, MD, a resident in Cleveland Clinic’s Glickman Urological & Kidney Institute and first author of the study, says this ambiguity led to a multi-institutional collaboration with colleagues at Mayo Clinic that helped jumpstart this investigation and others.
“These histologies are very rare and all previous literature comes from small single-institution series.”
Together the teams partnered to create a larger database of patients with variant histology undergoing radical cystectomy than has previously been reported. They decided which histologies to include – urothelial, sarcomatoid, small cell carcinoma, nested, micropapillary and plasmacytoid – and determined pathologic downstaging after neoadjuvant chemotherapy would be a clinically meaningful endpoint.
“Downstaging occurred if the pathologic tumor stage at the time of radical cystectomy was lower than the clinical tumor stage, established at the time of transurethral resection of the bladder tumor,” she explains.
Advertisement
Their analysis included 889 patients, 303 with variant histology and 586 non-variant histology patients, all of whom underwent radical cystectomy from 1980 to 2018. Patients with variant histology were matched with pure urothelial carcinoma patients by age, sex, clinical tumor and nodal stages, year of radical cystectomy and receipt of the neoadjuvant chemotherapy.
“Our primary finding is that patients with variant histology can respond to neoadjuvant chemotherapy, demonstrated by pathologic downstaging,” Dr. Campbell says.
“Patients with pure urothelial carcinoma showed pathologic downstaging, which reinforces the role of neoadjuvant chemotherapy in their clinical management, and the matched variant histology cohort had strikingly similar rates.”
The rates of downstaging across variant histology subgroups varied, which should be considered, but Byron Lee, MD, PhD, senior author of the study and urologic oncologist in the Glickman Institute, says these findings provide a basis for broader integration of neoadjuvant therapy for this patient population going forward.
“This could mean potentially improving outcomes for select patients,” he says. “It answers some unknown questions in the management of these patients and opens the door for broader, multi-institutional collaborations to better understand this rare and comparatively aggressive pathology.”
Advertisement
Advertisement

Adding 177Lu-PSMA-617 to ADT plus an ARPI cut the risk of radiographic progression or mortality by 28%

New program will help patients improve fitness and manage weight after cancer treatment

Cleveland Clinic hematologist highlights new guidelines and treatment advances in immune thrombocytopenia

NIMBLE replaces weekly tumor board delays with same-day multidisciplinary recommendations

Cleveland Clinic study provides validation for the test, which combines AI and pathological data to predict outcomes in postoperative patients

Advanced imaging technology catches metastases much earlier, allowing treatment with fewer side effects

Reduced radiation for lymph node areas reduces side effects

Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
 Search