Locations:


How the technology helped maintain transplant volume during a pandemic year
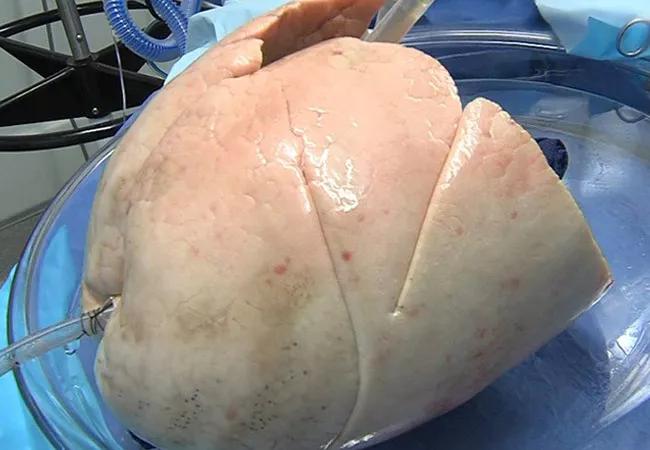
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/cf522136-7781-4e77-9fd2-9325d594c78a/21-HVI-2061015-ex-vivo-lung-perfusion_650x450_jpg)
photo of lungs being perfused on an ex vivo lung perfusion system
Cleveland Clinic’s ex vivo lung perfusion (EVLP) program is now the highest-volume program in the U.S. and growing rapidly. Whereas just 1% of Cleveland Clinic’s total lung transplants in 2016 involved lungs that underwent EVLP, that percentage rose to a robust 25% in 2020. In fact, the technology was instrumental in making Cleveland Clinic one of only four U.S. centers to perform more than 100 lung or heart-lung transplants during 2020 in the midst of the challenges of COVID-19.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Kenneth McCurry, MD, Surgical Director of Lung and Heart-Lung Transplantation, has been the leader of Cleveland Clinic’s EVLP efforts since they were initiated a decade ago. Consult QD caught up with him to discuss what EVLP brings to lung transplantation and emerging developments in the field.
A: Donor lungs remain in high demand, with many patients dying while waiting for organs. Unfortunately, only 20% of available donor lungs are actually used, despite acceptance of marginal donors and aggressive donor organ management. EVLP allows us to increase the pool of organs, helping to close the wide gap between supply and demand.
It does so in three main ways. First, a donated lung can be preserved outside the body while it is better evaluated to determine its likelihood to function successfully after transplantation. Second, lungs that are truly marginal for transplantation can be treated with techniques and therapeutic agents to improve function and make them transplantable after EVLP. Third, the extended organ preservation provided by EVLP allows assessment and utilization of organs that would otherwise go unused due to logistical factors such as last-minute organ offers.
One surprising role of EVLP we have discovered is that it allows us to determine that a lung that appears promising by traditional criteria may not, in fact, be suitable for transplantation. On rare occasions we have an organ that, despite meeting all the standard requirements, is found through EVLP assessment to have problems that would make it likely to fail. Because of this, EVLP has spared a few patients the experience of undergoing an ultimately unsuccessful transplantation.
Advertisement
For those interested in more detail, our team has summarized the fundamentals of EVLP in a review article in Current Transplantation Reports (2019;6:251-264).
A: We have conducted considerable research on how best to assess lungs for likelihood of successful function after transplantation. We developed a technique utilizing ultrasound to assess lungs undergoing EVLP called CLUE (DireCt Lung Ultrasound Evaluation), which is described in the Journal of Heart and Lung Transplantation (2020;39:1220-1227). It is a highly sensitive method of assessing extravascular lung water content, which correlates well with lung suitability for transplant.
We have also investigated methods of saving marginal lungs. One study evaluated the role of EVLP in salvaging lungs from donors with a high body mass index, which tend to have more atelectasis and a lower PaO2/FiO2 ratio. We found that using an aggressive protocol with EVLP can allow transplantation of some of these lungs, resulting in good outcomes (Ann Thor Surg. 2020;109:1663-1669).
Therapeutic interventions administered while a lung is on EVLP — to optimize organ function and resilience and reduce the likelihood of recipient rejection — are also being explored by us and other groups. Current topics of investigation include use of antibiotics to treat infection, as well as use of other biologic agents, including gene therapy, which can be inhaled by or injected into a donor organ while on EVLP. At Cleveland Clinic, we are focused on the potential benefits of therapies — including nitric oxide, nitrite and others — that are important to the immune response and may make the lung more resistant to rejection.
Advertisement
A: Having this program has benefited our lung transplant program enormously. Since the challenges of COVID-19 began early last year, EVLP has significantly enhanced our ability to maintain a good organ supply, which helped us perform 118 lung transplants in 2020, one of the highest volumes in the nation.
But such a program can’t be undertaken successfully without resources and commitment. The equipment and personnel costs are considerable. At Cleveland Clinic, we are fortunate to have strong institutional support that provides the necessary funding, dedicated staff and space. We are also fortunate to have an outstanding team — including Toshihiro Okamoto, MD, PhD, Associate Director of EVLP, and Kamal Ayyat, MD, PhD, Assistant Director of EVLP — who help provide great leadership, as well as fellows, respiratory therapists and perfusionists who contribute greatly to the team effort.
Experience is the other critical factor. Since our program started in 2016, we have performed more than 70 lung transplants involving EVLP, with 100% survival at 30 days and 93% survival at one year. This level of experience is invaluable for acquiring the ability to make good clinical decisions surrounding EVLP.
One of our goals is to assist others, and we have conducted several on-site education programs on EVLP for international and domestic transplant centers. In 2019, we initiated an annual EVLP symposium to bring together transplant clinician leaders, transplant center financial leaders and organ procurement organization leaders to discuss the financial, logistical and experience hurdles that are currently an impediment to broader application of this technology. We hope these efforts will make more lungs available for transplantation and save more lives.
Advertisement
Advertisement
Medical and surgical perspectives on the condition’s many high-risk scenarios
New review proposes a multimodality framework for matching patients to procedures
In-depth live symposia in Florida and Cleveland feature interdisciplinary experts from around the nation
Early results for ARO-DIMER-PA point to a more streamlined way to treat mixed hyperlipidemia
Findings support further studies of potential one-time treatment strategy
But unexpected results are ‘not the end of the story’ for Lp(a) lowering, investigators say
A scannable snapshot of recent volumes and results
Earlier detection is reshaping timing and safety of these increasingly common surgeries
 Search