Locations:


International registry study finds SEEG involves less morbidity, greater chance of seizure freedom

Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/3626796d-7985-44b2-9103-77e22fee9f31/NEU_2865231_06-02-22_028_LDJ)
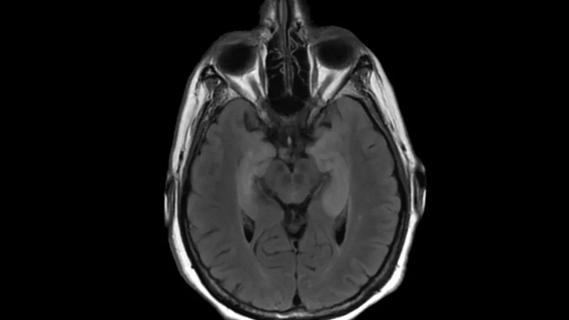
SEEG
Compared with stereotactic electroencephalography (SEEG), subdural electrode (SDE) evaluation of patients with drug-resistant epilepsy is likelier to lead to therapeutic resection but entails more surgical complications and is less likely to result in freedom from seizures. So concludes an international team of investigators who analyzed a large registry of patients who underwent either of these procedures.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
The study, published online in the Annals of Neurology, provides the strongest evidence to date comparing these two intracranial procedures for epilepsy localization.
“Our robust statistical approach using propensity score matching enabled us to create comparable treatment arms from registry data,” says first and corresponding author Lara Jehi, MD, an epileptologist and Chief Research Information Officer at Cleveland Clinic. “The results provide us with the highest feasible evidence level to guide decisions on using these invasive tools.”
While resection is the best treatment for drug-resistant focal epilepsy, a surgical plan cannot always be developed using noninvasive tests. In such cases, the following two major approaches are available to obtain intracranial EEG recordings:
Both approaches require complex technical resources and are associated with significant risks and costs as well as prolonged hospitalization. Because they also require different neurosurgical expertise and technical support, not many institutions offer both options. And programs that do have the capability for both tend to develop particular expertise in one, giving their providers a strong preference for that option.
Advertisement
“Clinical practice in this realm is preference-sensitive rather than evidence-based,” Dr. Jehi observes. “But obtaining evidence through a randomized clinical trial comparing the two methods is virtually impossible.” She cites two major reasons for this situation: only a few programs offer both procedures, and patients often have strong preferences about which method they want.
Although a few retrospective descriptive case series comparing the two methods have been published, the patient cohorts are generally too different at baseline to allow for meaningful comparisons, Dr. Jehi notes. She adds that this reflects the belief — based on expert consensus recommendations with no available class 1 or 2 evidence — that specific clinical settings are better suited to one method over another.
The study drew from an international registry governed by the Surgical Therapies Commission of the International League Against Epilepsy. The registry was created under Dr. Jehi’s leadership as commission chair to study outcomes of patients with drug-resistant epilepsy undergoing intracranial EEG. The 10 participating sites, including Cleveland Clinic, were selected to ensure uniformity in neurosurgical standards. Patients were at least 16 years old at the time of surgical evaluation and were followed for at least one year after evaluation.
The cohort consisted of 526 patients who underwent SDE and 942 who underwent SEEG between 2005 and 2019. Of the total of 1,468 patients, 988 (67%) underwent subsequent resection.
Advertisement
Propensity score matching was used to create statistically comparable cohorts to approximate a randomized clinical trial using observational data. Eighteen variables were used in the analyses of resection and seizure outcomes (e.g., seizure frequency, MRI findings, age and epilepsy duration); eight variables were used in the analysis of complications.
Analyses of propensity-matched groups revealed the following differences in outcomes between the two methods:
Although propensity matching allows for controlling of many variables, Dr. Jehi emphasizes that it is impossible at this point to conclude that one method is preferable in all cases. Some patients are more risk averse, while others are unwilling to delay surgery or undergo two hospitalizations. In addition, certain clinical scenarios — e.g., involving the likely location of a lesion — may also help determine the best evaluative approach.
“Our findings of the superiority of one method over another should inform decision-making but do not override other factors, such as local expertise and patient circumstances,” Dr. Jehi concludes. “The most important considerations are accomplishing surgery expeditiously and safely.”
Advertisement
She adds that additional studies using these statistical techniques are expected to further clarify choices when randomized clinical trials are not feasible.
Advertisement
Advertisement

Housing multidisciplinary clinicians in one leading-edge facility can transform GME along with patient care
How ongoing efforts will be bolstered by Cleveland Clinic’s new Neurological Institute building
Foundation model reveals latent risk structures in sleep physiology that elude conventional metrics

Where the field is moving and what Cleveland Clinic has in the works
Expanded bevy of dedicated ORs will feature customized designs, leading-edge technology, optimized workflows
Research could lead to bionic devices that work more like the human body

Multicenter study offers guidance on when to consider extended monitoring
Findings may have implications for understanding the disorders’ pathophysiology
 Search