Locations:


Guidance and facts for reassuring reluctant parents
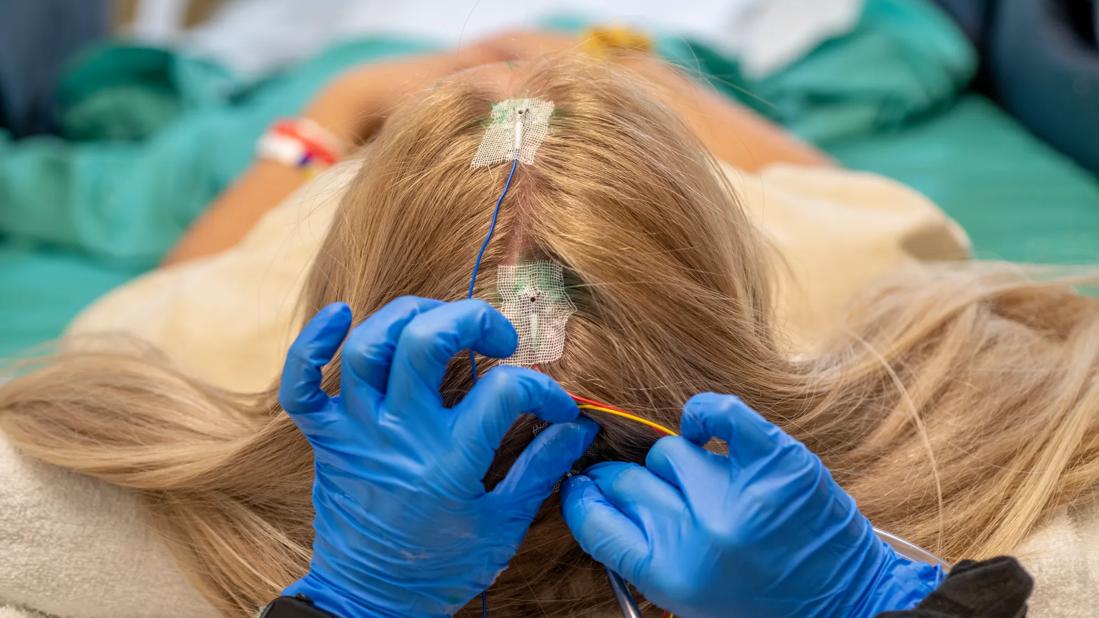
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/88de17eb-ccb9-4d69-99bf-a505751610a1/NEU_2865231_06-02-22_030_LDJ)
19-HHB-1245-emu-pediatric-650×450
By Ahsan Moosa Naduvil Valappil, MD
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Approximately one-third of patients with epilepsy experience uncontrolled seizures; in over half of those cases, the seizures have focal onset. Taken together, these two facts suggest that epilepsy surgery may be a promising option for a significant number of the 3.4 million Americans who have active epilepsy, yet research indicates that epilepsy surgery is performed for only a small fraction of those who could benefit. Even when surgery is eventually performed, in many cases it has been unnecessarily delayed for a decade or more. When such a delay occurs in children, it may result in lasting deleterious effects on cognitive and behavioral development.
To counter this underutilization of epilepsy surgery, many child neurologists are increasingly thinking about surgical options earlier rather than later. If a child continues to have seizures despite adequate trials of two appropriate medications at optimal doses, the next question should be whether the child is a surgical candidate. In children with drug-resistant epilepsy, clues to surgical candidacy include the following:
If any of these features is present, referral to a specialized pediatric epilepsy surgery center may be appropriate.
When broaching this difficult topic, child neurologists may encourage parents to think about epilepsy surgery as a possible safe “third step” in the treatment plan (after failure of two medication trials) rather than as a risky last resort. Several points may be helpful in this critical conversation.
Advertisement
1) For carefully evaluated patients who qualify, the success rate for epilepsy surgery is high. For example, at Cleveland Clinic, where more than 400 epilepsy surgeries are performed each year, 60% of patients who undergo these operations remain free of seizures even after many years. In contrast, if two or more drugs have already failed, the chance that any further medications will lead to sustained reduction of seizures is less than 10%.
A 2017 report from India illustrates this point dramatically.1 Researchers studied a group of children with drug-resistant epilepsy, half of whom had surgery and half of whom received medical therapy alone while on a waiting list for surgery. Twelve months later, 77% of the surgically treated children were seizure-free, compared with only 7% of the children treated with medicine alone. Clearly, surgery provided vastly superior results.
2) With today’s sophisticated imaging and surgical techniques, the risks of epilepsy surgery are very low. Patients considering surgery at an advanced epilepsy center can anticipate a safe experience and full recovery. With regard to the most serious epilepsy-related lifelong risk of all — sudden unexpected death — epilepsy surgery may actually have a protective effect. Research has shown that surgery is associated with a significant reduction in mortality in patients with drug-resistant epilepsy, especially when seizures are abolished altogether or when generalized tonic-clonic seizures are reduced.2
3) Stopping seizures with surgery can be life-changing. Benefits include a lower risk for accidents and physical injury; greater opportunities for driving, employment, family life and independence; and a lower risk for psychological effects such as depression and anxiety. Some children even experience improved academic performance once seizures have ceased or decreased and medications are reduced. The sooner these benefits are realized, the better — for both the child and the entire family.
Advertisement
If sooner is generally better when it comes to epilepsy surgery for appropriate candidates, when does one know exactly when the time is right? Three questions should be considered with regard to timing in every case:
To minimize the negative effects of seizures and medications, the optimal timing for surgery may be the soonest time that all three of these questions can be answered in the affirmative.
By identifying opportunities for surgery early in the clinical course, encouraging evaluation at an epilepsy surgery center and helping families feel comfortable with the plan, child neurologists today are well-positioned to help more patients with drug-resistant epilepsy than ever before.
Dr. Wyllie is Professor of Medicine, Cleveland Clinic Lerner College of Medicine. Both she and Dr. Naduvil Valappil are pediatric neurologists in Cleveland Clinic’s Epilepsy Center.
Advertisement
Advertisement

Milestone case report expands understanding of infectious risks for those on immunomodulatory therapies

Advanced technologies are changing expectations about what’s possible

A rare opportunity to design for speed, care coordination, recovery and continuous monitoring
Multidisciplinary, proactive approach also improved discharge outcomes
Phase 1 Breakfree-2 trial reports good safety and efficacy at week 26

Inflammatory protein eotaxin-1 may be a marker of future cognitive decline

Therapists and physicians collaborate to get medically stable patients moving

Designed for digitization, distance health, discovery and more
 Search