Locations:


Late diagnosis means significant opportunity for intervention is lost
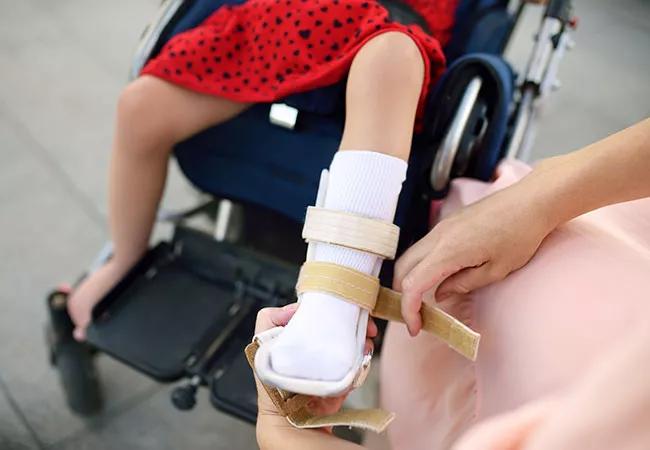
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/4638f9ea-6d9e-4dc4-bf95-82e7ae783d58/650x450-Holman-Cerebral-Palsy-Pediatric-Rehab_jpg)
650×450-Holman-Cerebral-Palsy-Pediatric-Rehab
Despite proven benefits of early diagnosis – before 12 months of age – of cerebral palsy (CP), only about 21% of children in high-income countries are currently being diagnosed early, says Lainie Holman, MD, a pediatrician in the Department of Developmental and Rehabilitation Pediatrics at Cleveland Clinic Children’s Hospital for Rehabilitation.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Early diagnosis of CP, even if incorrect, has many advantages for a child and few disadvantages, reports Dr. Holman. “By diagnosing a child before one year of age, which is considered early since the disorder is traditionally diagnosed between 12 and 24 months, you can maximize motor and cognitive outcomes and minimize complications such as hip dislocation, scoliosis and spasticity,” she says. “And if you get the diagnosis wrong, you may cause the parents some distress, but nothing bad will happen. The interventions are unlikely to cause harm, and will probably promote development even if a child is not ultimately diagnosed with CP.” In addition, early diagnosis does not preclude a search for etiology or confirmation.
Dr. Holman recently conducted a virtual grand rounds for general pediatricians at Cleveland Clinic to review new early diagnosis guidelines released by the American Academy of Cerebral Palsy and Developmental Medicine (AACPDM) in May 2020. “These guidelines suggest that diagnosis can be made before five months of age with a high degree of accuracy,” she notes. In fact, the AACPDM guidelines state that “it is not good practice to offer conservative ‘wait and see’ monitoring” because early interventions offer the greatest opportunities for gains in neuroplasticity. “If diagnosis is delayed, infants with CP will not be using their motor cortex and risk loss of connections,” Dr. Holman says. Likewise, delayed motor behavior will not promote growth and development the way it does in children without CP.
Advertisement
Parents also typically benefit from an early diagnosis, and are less likely to experience depression and stress and to be dissatisfied with the diagnostic process than parents of children diagnosed later.
Prior to five months of age (corrected for prematurity), diagnosis can be performed via history, administration of the Gross Motor Assessment (GMA) and a magnetic resonance imaging (MRI) scan if deemed necessary, safe and affordable. After five months (also corrected for prematurity), the Hammersmith Infant Neurological Exam (HINE) should be used instead of the GMA.
“The GMA is scored based on writhing and fidgety movements,” she says, noting that it is “astonishingly sensitive at 98%.” It is routinely performed in the NICU, but can also be scored by a trained therapist after viewing a video of the baby.
The Hammersmith is 90% sensitive, and contains 34 items to assess tone, motor patterns, spontaneous movements, reflexes and visual/auditory attention and behaviors. MRI is 86% to 89% sensitive, but unpopular due to the need for sedation. The AACPDM guidelines state that the combination of the three tests is most accurate, but early diagnosis can still be made with confidence based on history and results of the GMA or HINE depending on the child’s age.
Dr. Holman encourages pediatricians who are hesitant to make an early diagnosis to note a high risk of CP in a patient’s chart or to refer the patient to a neurologist or physiatrist for evaluation, again emphasizing that if the diagnosis is not made until the child is two years old and when the clinician can be absolutely sure of its accuracy, a significant window of opportunity for early intervention will be missed. “Once a lesion develops, it can’t be reversed, although we can improve quality of life (QOL), cognition, mobility and things that flow from those deficits, such as hip dislocation,” she says.
Advertisement
Early interventions should be intense, enriched and task specific, she says, and should focus on optimizing motor, cognitive, communication and activities of daily living/feeding outcomes using methods that promote neuroplasticity. Efforts should also be directed toward preventing and monitoring for secondary impairments and complications, such as hip dysplasia/subluxation, which affects more than one-third of patients with CP, as well as sleep, oral, vision, hearing and swallowing disorders. In addition, “these children should be encouraged to engage in exercise and adaptive sports for overall health, to build social skills, make friends and improve QOL,” she says.
Importantly, early intervention should also promote caregiver coping and mental health. “Positive parenting programs, Acceptance and Commitment Therapy and individual counseling are all beneficial, and parents receive a great deal of information about CP from therapists,” she reports.
“While CP isn’t life threatening, its severity varies, and outcomes can and should be improved by early diagnosis and targeted, evidence-based interventions,” concludes Dr. Holman.
Advertisement
Advertisement

A rare opportunity to design for speed, care coordination, recovery and continuous monitoring
Multidisciplinary, proactive approach also improved discharge outcomes
Phase 1 Breakfree-2 trial reports good safety and efficacy at week 26

Inflammatory protein eotaxin-1 may be a marker of future cognitive decline

Therapists and physicians collaborate to get medically stable patients moving

Designed for digitization, distance health, discovery and more

Combining customized care, research capabilities and flexibility for the future

Leading investigators outline a new roadmap for clinical trials and observational research
 Search