Locations:


Large Cleveland Clinic analysis may help resolve a longstanding question over optimal fractionation
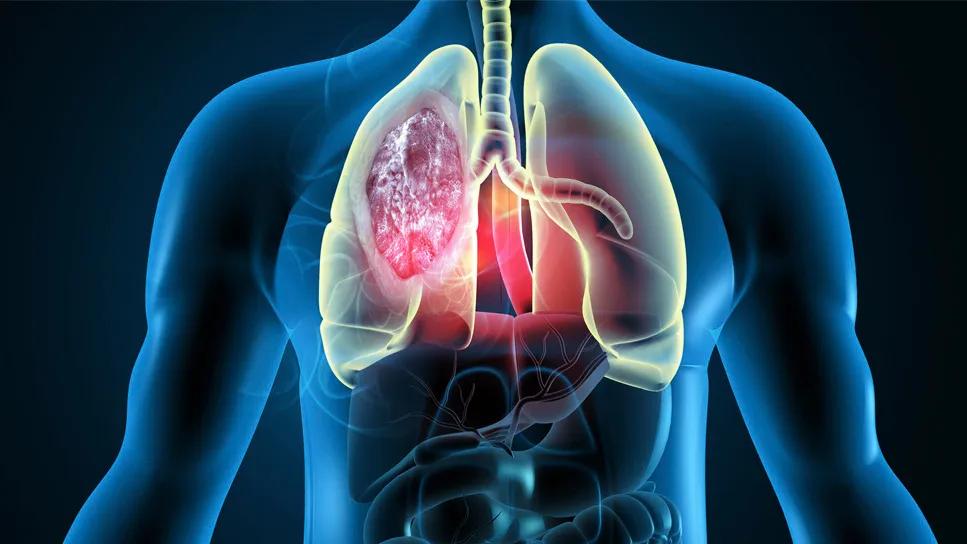
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/6ba06dd3-39b9-49f7-8bc9-d5fe860269fb/illustration-of-lung-cancer-2257364472)
Lung cancer illustration
For patients with inoperable early-stage lung cancer, stereotactic body radiation therapy (SBRT) has transformed treatment by delivering potentially curative radiation in a fraction of the time required with conventional radiation therapy. But even as treatment courses have shortened, one question has remained: How many fractions are actually necessary?
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
A Cleveland Clinic analysis of more than 1,100 patients suggests that a single fraction may achieve outcomes comparable to a three-fraction regimen, with no significant differences in overall survival, patterns of failure or serious toxicity, according to findings presented at the 2026 American Society for Radiation Oncology (ASTRO) Annual Meeting.
“From a patient’s perspective, the idea that you can come in and get treated in a single shot has been mind-blowing,” says study author Gregory Videtic, MD, a staff physician with Cleveland Clinic’s Thoracic Radiation Oncology department. “At the beginning, just getting five treatments was amazing. Now we’re talking about one.”
SBRT has become an established treatment for medically inoperable early-stage lung cancer, offering high rates of local control with a short treatment course. However, the optimal fractionation schedule has remained less clearly defined, with regimens ranging from a single fraction to several treatments.
Cleveland Clinic was an early adopter of lung SBRT and participated in national trials evaluating different fractionation approaches. Dr. Videtic previously served as principal investigator of the NRG Oncology RTOG 0915 trial, which compared single-fraction SBRT with a four-fraction regimen.
The next step was intended to be a phase 3 RTOG trial comparing the single-fraction regimen from RTOG 0915 with the three-fraction regimen used in RTOG 0236. The proposed primary endpoint was three-year overall survival. Despite extensive planning, the trial was never activated. And without a definitive phase 3 comparison, practices have continued to use a range of SBRT schedules. Although there is evidence supporting single-fraction SBRT, broader adoption has remained limited, in part because of persistent concerns that delivering treatment in a single fraction could increase toxicity.
Advertisement
After years of using the approach at Cleveland Clinic, Dr. Videtic and his colleagues realized their prospective lung SBRT registry offered an opportunity to revisit the unanswered question.
The retrospective analysis included 1,107 patients with inoperable peripheral early-stage lung cancer treated with SBRT at Cleveland Clinic between 2003 and 2025. Of these, 685 (61.9%) received single-fraction SBRT at 34 Gy and 422 (38.1%) received three-fraction SBRT at either 60 Gy or, with heterogeneous planning, 54 Gy.
The groups were similar in patient and tumor characteristics. The median age was 73.5 years, median Karnofsky Performance Status was 80 and 54.5% of patients were considered inoperable because of pulmonary comorbidities. The median tumor size was 1.8 cm, and 77.5% of cancers were biopsy confirmed.
Median overall survival was 44.4 months with single-fraction treatment and 44.2 months with three fractions. Three-year overall survival was nearly identical at 57.7% and 57.6%, respectively. The five-year overall survival was 38.0% versus 40.9%. The difference in overall survival was not statistically significant (P = 0.27).
Patterns of failure were similarly comparable. At five years, local failure occurred in 4.5% of the single-fraction group and 3.0% of the three-fraction group (P = 0.15), while distant failure occurred in 21.4% and 24.0%, respectively (P = 0.21).
Grade 3 or higher toxicity occurred in 2.8% of patients overall, with no significant difference between fractionation schedules (P = 0.40). Grade 3 or higher chest wall toxicity occurred in 0.4% of patients receiving one fraction and 0.7% receiving three. Each group had one grade 5 event, both of which were attributed to pneumonitis.
Advertisement
Multivariable analysis found no patient, tumor or treatment factors associated with local or distant failure by fractionation schedule. Overall survival was significantly associated with age at SBRT, performance status, sex and tumor size.
“This large single institution analysis of nearly 1,100 patients revealed no differences in overall survival between single-fraction and three-fraction lung SBRT patients and specifically none at the proposed RTOG phase III endpoint of three-year overall survival,” Dr. Videtic and colleagues conclude. “Local failure, distant failure and grade 3 and higher toxicity rates [including chest wall] were similar between fractionation schedules. This suggests that single-fraction should be the standard lung SBRT option for inoperable early-stage lung cancer.”
The implications extend beyond tumor control and toxicity. Reducing three treatment visits to one can lessen the burden on patients, an important consideration in an older, medically fragile population. There may also be broader implications for healthcare utilization and cost, although those outcomes were not evaluated in the current study.
Dr. Videtic sees the findings as part of a larger movement in radiation oncology toward shorter treatment courses when comparable outcomes can be maintained. The next questions, he adds, may extend beyond fractionation itself. Researchers are already examining how SBRT can be integrated with systemic therapies and how it compares with surgery in broader populations with early-stage lung cancer.
Advertisement
“My hope is that these findings give clinicians greater confidence in single-fraction treatment,” Dr. Videtic notes. “We now have a very large experience showing that we can achieve the same cancer outcomes without compromising safety, while offering patients the advantage of completing treatment in a single visit.”
Advertisement
Advertisement
This single-port option offers advantages for appropriate patients

Practice changes needed to expand access across academic and community settings
Treatment yields positive results despite late diagnosis and cardiac involvement

Early detection program integrates multiple disciplines to reduce screening barriers and patient anxiety
Newer class of medications evolves care models for patients with hemophilia

Improving access to specialists
Dotatate PET/CT scan and molecular testing informed treatment trajectory

A proactive, framework-based approach
 Search