Locations:


Insights on the PROTECTED TAVR and WATCH-TAVR trials
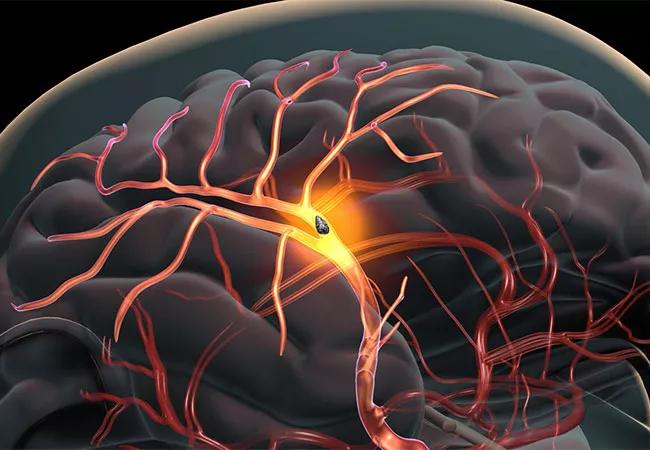
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/0401e2c7-052a-4607-ba1f-6e28ceb172a1/20-HVI-1921580-stroke-risk-650x450-1_jpg)
20-HVI-1921580-stroke-risk-650×450
Despite advances in device technology and improved operator experience, the rate of stroke following transcatheter aortic valve replacement (TAVR) has remained steady, at just under 2.5%, since 2012 (JAMA. 2019;321:2306-2315). Moreover, 30-day mortality among TAVR patients who have a stroke is approximately 15%, and about two-thirds of these patients die within a year of their stroke. Survivors do not fare well, either: 70% are discharged to a nursing home, and 44% suffer moderate to severe permanent disability.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
“Post-TAVR stroke is not a minor issue,” says Samir Kapadia, MD, Chair of Cardiovascular Medicine at Cleveland Clinic. “We must bring the stroke rate down.”
Cerebral embolic protection devices are the most obvious solution. The Sentinel™ Cerebral Protection System, a downstream filter designed to capture and remove thrombi and debris, is the only such device currently approved in the U.S. However, the Centers for Medicare & Medicaid Services (CMS) does not reimburse for the device, citing insufficient efficacy data. As a result, only 25% of TAVR centers in the U.S. routinely use the device.
Cleveland Clinic is one of those centers. Its TAVR team performs some 700 TAVRs a year and attempts to use the Sentinel device in all TAVR patients.
“Our post-TAVR stroke rate is 0.2%, compared with about 2.5% nationally,” says Amar Krishnaswamy, MD, Section Head of Invasive and Interventional Cardiology. “We believe the device is tremendously effective.”
Questions about the device’s efficacy stem from the lack of a statistically significant reduction in the primary endpoint of the pivotal trial — i.e., brain emboli on MRI. However, there was a 63% risk reduction in clinical stroke among patients receiving the device, which is consistent with the reduction in clinical stroke (60% to 80%) seen in many large, single-center analyses of the device, Dr. Krishnaswamy notes. “That is why a new trial focused on clinical stroke rate, which is most relevant to patients and healthcare providers, is necessary,” he adds.
Advertisement
Cleveland Clinic hopes the multicenter PROTECTED TAVR trial (NCT04149535) will supply the robust data CMS and TAVR operators need to get on board with the device.
“With 3,000 patients being randomized to TAVR with or without Sentinel, PROTECTED TAVR is large enough to detect a clinical reduction in stroke at 72 hours,” says Dr. Kapadia, who designed the trial and is serving as national principal investigator. “Since only 25% of patients undergoing TAVR receive an embolic protection device at the time of the procedure, we plan to enroll in sites that do not routinely use the device.”
If PROTECTED TAVR yields results that confirm efficacy for stroke prevention, CMS is expected to reimburse for the device. These two developments would likely boost adoption of the device. “Most TAVR programs walk a fine line between breaking even and losing money, and the cost of this device may be prohibitive,” notes Dr. Krishnaswamy.
The trial is scheduled for completion in mid-2022.
Cleveland Clinic researchers are at the fore of another multicenter trial evaluating embolic protection during TAVR, this time in the setting of simultaneous placement of the Watchman™ left atrial appendage occlusion device for reduction of stroke risk from atrial fibrillation (AF).
About 30% of patients with aortic stenosis have coexisting AF. However, the combination of TAVR and Watchman implantation in a single procedure has been discouraged by policies that prohibit reimbursement for the Watchman device in this setting.
Advertisement
“We would like to combine the procedures so that these patients aren’t subjected to the extra risk, cost and inconvenience of undergoing two separate procedures,” says Dr. Kapadia.
The multicenter WATCH-TAVR trial (NCT03173534), for which Dr. Kapadia is national principal investigator, was designed to show the FDA and CMS that implanting both devices in a single procedure is both safe and financially prudent.
The trial is randomizing 312 patients at approximately two dozen U.S. centers to TAVR plus either anticoagulation or Watchman implantation. It is on target for completion late this year.
“We expect to see a reduction in bleeding and stroke when patients are off anticoagulants,” says Dr. Krishnaswamy. “We also expect there will be savings by combining the procedures, because the only difference will be the additional cost of the device.”
Two additional neuroprotective devices for use during TAVR have completed clinical trials, but no results have been published to date.
One is an embolic deflector, called TriGuard 3™. It deflects emboli from entering the cerebral circulation. The other is a filter that works on the same principle as the Sentinel device.
Other clinical trials are taking a different approach by evaluating whether anticoagulants can prevent formation of small clots on the TAVR valve that tend to break off and cause stroke. These trials have been completed, but no results have been published.
“We’re awaiting the data from new devices for stroke prevention but aren’t sure how this will play out because it depends on the safety and efficacy of these devices,” says Dr. Kapadia.
Advertisement
Advertisement
In-depth live symposia in Florida and Cleveland feature interdisciplinary experts from around the nation
Early results for ARO-DIMER-PA point to a more streamlined way to treat mixed hyperlipidemia
Findings support further studies of potential one-time treatment strategy
But unexpected results are ‘not the end of the story’ for Lp(a) lowering, investigators say
A scannable snapshot of recent volumes and results
Earlier detection is reshaping timing and safety of these increasingly common surgeries
Bench-to-bedside study identifies mechanism and potential therapeutic target
Integrating research and clinical care can yield reciprocal rewards
 Search