Locations:


The procedure is safe, but prepare for AF recurrence rates approaching 50%
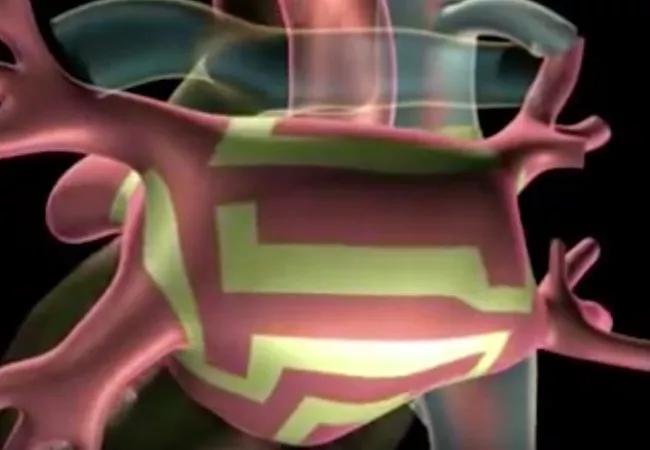
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/477760be-6d56-4df8-99ca-e09112287ecb/21-HVI-2067663-surgical-ablation-atrial-fibrillation_650x450-1_jpg)
anatomic illustration of heart showing maze procedure
Surgical ablation of atrial fibrillation (AF) at the time of septal myectomy for hypertrophic obstructive cardiomyopathy (HOCM) is safe but is associated with AF recurrence within five years in nearly half of patients. So reports a team of Cleveland Clinic clinicians in one of the first studies to assess concomitant surgical ablation of AF in patients undergoing myectomy.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Leading predictors of AF recurrence were left atrial enlargement, older age and lower preoperative resting left ventricular outflow tract (LVOT) gradient, according to the study, published recently in the Journal of Cardiac Surgery (2020;35:2957-2964).
“In spite of an aggressive approach to AF in this population, we observed recurrence in 48% of patients at five years, which is much higher than the 15% to 30% recurrence reported following surgical ablation in patients with stand-alone or valvular AF,” says the study’s first author, Kevin Hodges, MD, a cardiothoracic surgery resident at Cleveland Clinic.
“Patients with HOCM are at considerable risk of developing new-onset AF, which is often associated with worsening heart failure as a result of compromised left ventricular diastolic filling,” notes study co-author Nicholas Smedira, MD, a Cleveland Clinic cardiothoracic surgeon. “Yet data on concomitant surgical ablation for AF in patients undergoing myectomy are limited. We undertook this study to better define the optimal approach to concomitant AF ablation in this setting.”
The researchers retrospectively reviewed 1,549 patients who underwent surgery for LVOT obstruction by a single surgeon (Dr. Smedira) from 2005 through 2015. They identified 142 operations that included concomitant ablation for AF. Because most HOCM patients at Cleveland Clinic are referred from a distance and not followed after the early postoperative period, the researchers focused on a subgroup of 67 of these 142 patients (47%) who had follow-up that continued beyond three months.
Advertisement
The surgical ablation strategy was customized to the patient’s preoperative AF burden; high burden was defined as persistent AF or requirement for cardioversion. Patients underwent one of three ablation procedures:
The lesion set in each case was decided by the lead surgeon (Dr. Smedira) at the time of surgery. The primary endpoint was AF recurrence, and recurrence predictors were determined using random forest statistical methodology.
Preoperative AF burden was classified as low in 57% of patients and high in 43%. Patients with low burden most often underwent pulmonary vein isolation, whereas those with high burden most often underwent modified Cox-maze III or Cox-maze IV. Apart from AF burden, preoperative characteristics were comparable between the three ablation procedure groups.
All 67 patients experienced a significant reduction in resting and maximum LVOT gradient following surgery, more than three-quarters had 1+ or less mitral regurgitation on postoperative echocardiography, and 12% of patients underwent postoperative pacemaker placement.
Rates of AF recurrence over time were as follows:
Significant predictors of AF recurrence were lower resting LVOT gradient, larger left atrial diameter and older age. Notably, preoperative AF burden and lesion set did not predict AF recurrence.
“We had anticipated that surgical ablation of AF would be less effective in patients with HOCM than in those with valvular or stand-alone AF, so we treated these patients aggressively,” says Dr. Smedira. “Nevertheless, our findings that AF recurrence approaches 50% at five years should temper patient and physician expectations about the likelihood of long-term freedom from AF in this population.”
Advertisement
He adds that the finding that lesion set and preoperative AF burden were not related to AF recurrence suggests that the ablation strategy was well matched to the preoperative AF burden. “Surgeons are well advised to perform biatrial lesion sets in patients with high AF burden,” he notes.
In their study report, the researchers share several implications of their findings:
Finally, the fact that 43% of the study’s patients underwent concomitant mitral valve repair (n = 24) or replacement (n = 5) in addition to myectomy and surgical ablation underscores the need for broad expertise in managing this complex patient population. “Hypertrophic obstructive cardiomyopathy is a common condition that requires a nuanced and tailored team-based approach,” says study co-author Marc Gillinov, MD, Chair of Thoracic and Cardiovascular Medicine at Cleveland Clinic. “Decisions regarding the extent of the surgical myectomy and the need for a mitral valve procedure in these patients require input from both expert cardiologists and surgeons.”
Advertisement
Advertisement

AHA statement details nuanced, evidence-based strategies
The benefits of multiarterial grafting are possible without opening the chest

Collaborative citywide initiative reshapes protocols to boost cardiac arrest survival
For severe cases, complete unroofing of the bridge is imperative
Lower threshold expanded revascularization candidacy without raising early complication rates
Elevated levels of the gut microbial metabolite predict prevalence and adverse outcomes in community-based study
They generally depend on the mutated gene, clone size and clinical setting
Large analysis adds to evidence that absolute diameter alone may miss vulnerable patients
 Search