Locations:


Small pump can boost the heart to buy time
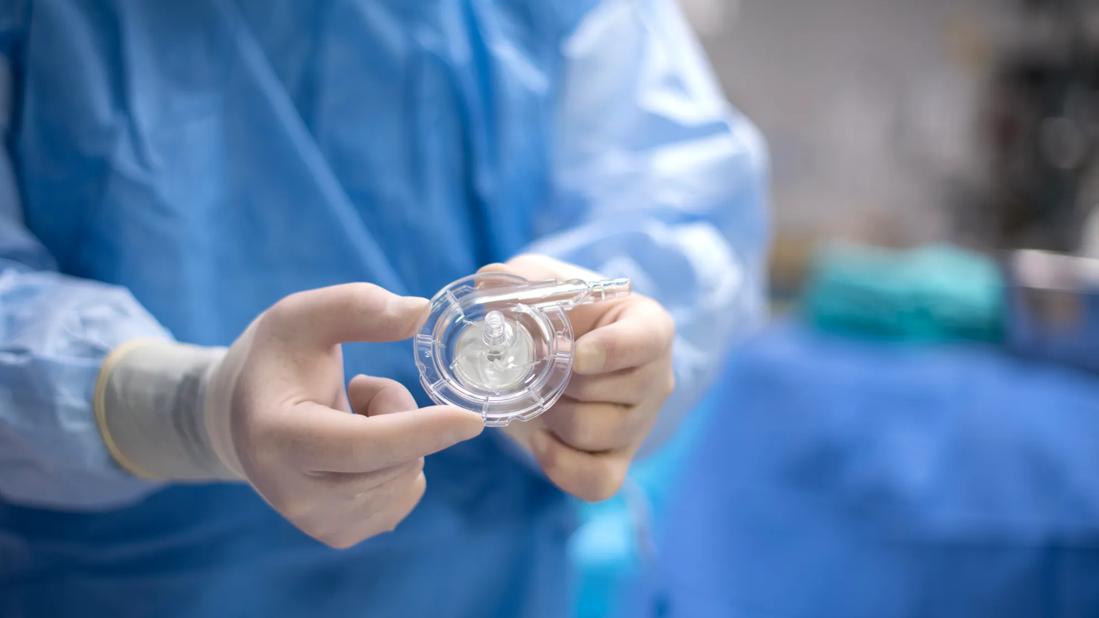
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/2775ad64-d033-40b0-b1d6-66bbdfeecdb5/ventricular-assist-device-pump)
Pediatric VAD
Children born with a single functional ventricle are palliated with a Fontan procedure, often by the age of 3. In the absence of one ventricle, this procedure reroutes venous blood to the pulmonary arteries for reoxygenation in the lungs.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
A large proportion of these children do well for years before needing a heart transplant. However, 20 to 30 percent may develop chronic venous hypertension leading to liver damage, making them ineligible for transplantation. In these patients, a ventricular assist device (VAD) can improve the Fontan circuit by boosting the single ventricle’s pumping power. This can improve the child’s health and buy valuable time.
“There is a common misunderstanding that when a Fontan fails, we can’t do anything for the patient. It’s important to know that this is not true. We have successfully bridged a lot of these patients to transplant with a VAD,” says Hani Najm, MD, Chair of Pediatric and Congenital Heart Surgery at Cleveland Clinic.
Cleveland Clinic Children’s has one of the most active pediatric VAD programs in the country. Last year, Dr. Najm and colleagues implanted eight VADs in children and adults with congenital heart defects or cardiomyopathies. Some patients were on the transplant list; others were not.
“We are one of few centers that will implant a VAD in someone who is not yet a transplant candidate. We have found they often improve when their heart is assisted. This makes them a better transplant candidate later on,” Cleveland Clinic Children’s Pediatric Cardiology Chair Elizabeth Saarel, MD, explains.
In addition to its small size that allows the VAD to be implanted in children weighing as little as 20 kg, the device is portable. As a result — and building on Cleveland Clinic’s vast experience with VADs in adults — the pediatric VAD program has added an outpatient component.
Advertisement
“We are one of only three centers in the country with this program,” says Dr. Saarel.
As soon as possible after surgery, the child is sent to Cleveland Clinic Children’s Hospital for Rehabilitation to begin the recovery process. The VAD’s cable, battery and power pack enable physical and occupational therapy to be conducted without hindrance. As the child grows stronger, the parents develop confidence in caring for the VAD and can look forward to returning home as a family.
VADs are only one component in an array of techniques and technologies for children whose Fontan fails. Options include repairing the defective valve or baffle or eliminating an arch obstruction to improve blood flow.
When a high transforming gradient results despite these efforts, a VAD may be considered.
Referring physicians are encouraged to contact Drs. Najm or Saarel for a consult as soon as a patient with a single ventricle begins to fail.
“We like to see patients sooner rather than later. Often we can do surgery — albeit complex — to prevent the need for a VAD or heart transplant. It’s our goal to ward off the worst outcome,” says Dr. Najm.
Advertisement
Advertisement

AHA statement details nuanced, evidence-based strategies
The benefits of multiarterial grafting are possible without opening the chest

Collaborative citywide initiative reshapes protocols to boost cardiac arrest survival
For severe cases, complete unroofing of the bridge is imperative
Lower threshold expanded revascularization candidacy without raising early complication rates
Elevated levels of the gut microbial metabolite predict prevalence and adverse outcomes in community-based study
They generally depend on the mutated gene, clone size and clinical setting
Large analysis adds to evidence that absolute diameter alone may miss vulnerable patients
 Search