Locations:


Devastating long-term effects in a young adult patient
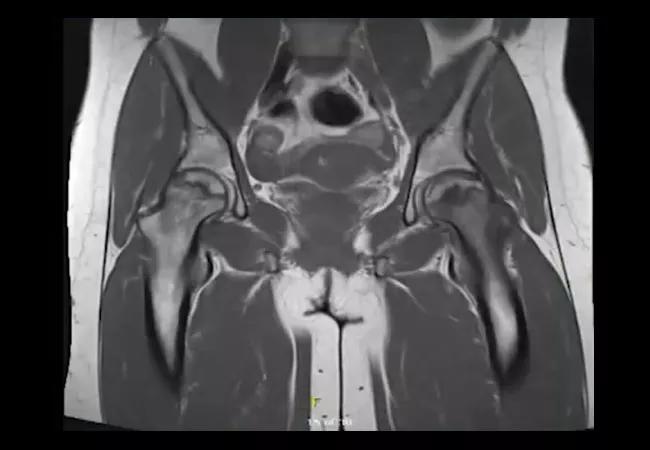
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/c59eb935-2acf-4efc-a583-de7c158b201c/21-RHE-2528452-Patient-with-Steroid-Toxicity-CQD_650x450_jpg)
21-RHE-2528452-Patient-with-Steroid-Toxicity-CQD_650x450
A 26-year-old female presented to the emergency department with polydipsia, polyuria and random glucose of 700 mg/dL. Her hemoglobin A1C was 7.5%, and she was diagnosed with diabetes. A bone densitometry test showed a Z score of -1.7 in the spine, less than expected for age.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
She had previously been diagnosed with autoimmune hepatitis and required high doses of intravenous steroids, azathioprine and tacrolimus. She also required a prolonged course of oral steroids. She eventually developed profound proteinuria and underwent a renal biopsy which showed membranous glomerulonephritis. Immunofluorescence showed a full house pattern. She had been referred to rheumatology, where her labs revealed high titer antinuclear antibodies, positive anti-Smith antibodies, normal anti-double stranded DNA antibodies, normal C3 and C4 and a normal complete blood count. She was later was diagnosed with systemic lupus with renal involvement and placed back on steroids with the addition of hydroxychloroquine.
In the emergency department, her hemoglobin A1C was 7.5%, and she was diagnosed with diabetes. A bone densitometry test showed a Z -score of -1.7 in the spine which is less than expected for age. At follow up, she presented with bilateral groin and hip pain, but X-rays did not show obvious avascular necrosis. Bilateral magnetic resonance imaging of the hips showed left-sided acute-on-chronic avascular necrosis and chronic avascular necrosis of the right femoral head with a right-sided joint effusion. She eventually required bilateral hip replacements. Watch as Emily Littlejohn, DO, MPH, staff in the Department of Rheumatologic and Immunologic Diseases, discusses the case.
Video content: This video is available to watch online.
View video online (https://www.youtube.com/embed/u1A4dFF66Rw?feature=oembed)
A Patient With Steroid Toxicity
“The issues highlighted by this case include the devastating long-term effects of steroids, including steroid-induced diabetes, bone density less than expected for age and osteonecrosis of the femoral heads,” says Dr. Littlejohn. “We need to be aware of the modifiable risks of steroid toxicity.”
Advertisement
Advertisement
Patient had tenolysis and fasciectomy but sympoms recurred
Best practices in a changing landscape
Case: Presentation includes joint pain and neurological symptoms
Evidence suggests empathy influences immune function and well-being
Going beyond simple referrals to streamline patient access

Tracing our understanding of this complex systemover more than a century

Drug-free remission holds more than a year after treatment

Cleveland Clinic group works toward earlier diagnosis of this rare disease
 Search