Locations:


Elevated levels of the gut microbial metabolite predict prevalence and adverse outcomes in community-based study
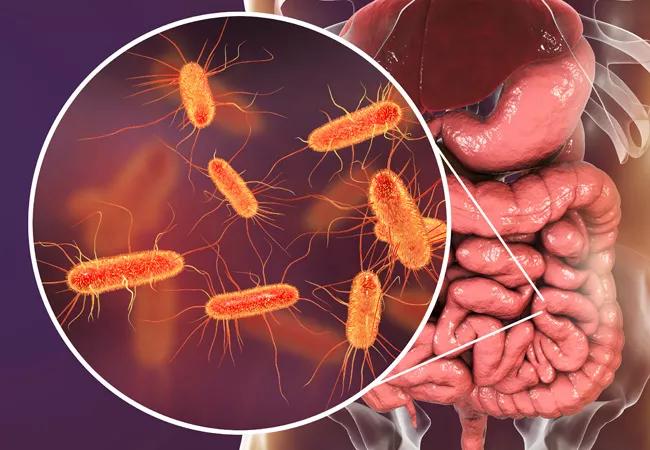
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/83a71998-0380-4521-9ecb-f47c323bacaa/20-HVI-1846765-Hazen-PAG-CQD-jpg)
human intestines with inset showing gut microbes
Managing abdominal aortic aneurysms (AAAs) generally involves some degree of watchful waiting. With no approved medical therapies available to stop progressive aortic dilation, clinicians must monitor smaller aneurysms until size-related thresholds justify the risk that may be involved with surgical repair.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Now, a study published in the European Heart Journal has identified a welcome new biomarker to help guide and refine the watch-and-wait process — and perhaps to target therapeutically. Analyzing data from the community-based Cardiovascular Health Study, researchers found that elevated plasma levels of trimethylamine N-oxide (TMAO), a metabolite produced by gut microbes from common dietary nutrients, are independently associated with baseline AAA prevalence and a significantly increased risk of future adverse aortic events, including aneurysm-induced death. The research was co-led by Cleveland Clinic and Tufts University.
“These findings support TMAO as a risk factor for abdominal aortic aneurysms and resulting adverse aortic outcomes,” says co-senior author Stanley Hazen, MD, PhD, Chair, Department of Heart, Blood and Kidney Research, Cleveland Clinic Research, and Co-Section Head of Preventive Cardiology at Cleveland Clinic. “They suggest that TMAO, which is measured through a readily available blood test, may be used to predict aneurysm risk even among apparently healthy elderly people.”
“Our findings have potential therapeutic implications too,” adds co-author Scott Cameron, MD, PhD, Section Head of Vascular Medicine at Cleveland Clinic. “In addition to the potential to block TMAO’s harmful effects at the blood vessel wall, there are opportunities to prevent the gut microbiome from facilitating TMAO production in the first place, either through diet or with existing or novel pharmacotherapies.”
Advertisement
AAA rupture represents an important cause of death in older adults. Because aneurysms remain asymptomatic until they rupture, early detection and precise risk modeling are crucial. Although blood pressure control and smoking cessation are highly recommended means of mitigating rupture risk, surgery remains the only definitive treatment option.
Extensive work by Dr. Hazen and Cleveland Clinic colleagues over the past 15 years has established the gut microbe-dependent TMAO metabolic axis as a significant contributor to risk for various cardiometabolic diseases. Dietary nutrients such as choline and carnitine, which are abundant in red meat, are metabolized by gut microbes into trimethylamine and then oxidized into TMAO in the liver. Preclinical work by the Hazen group and others shows that TMAO drives AAA development by promoting wall inflammation and cellular death.
Although earlier clinical analyses have focused on high-risk populations with established cardiovascular disease, the current study is the first to investigate whether repeated TMAO measurements predict long-term clinical AAA outcomes in a large, community-dwelling population of older adults.
The researchers analyzed data from the Cardiovascular Health Study, a prospective, community-based cohort. The sample included 4,442 community-dwelling older adults aged 65 years or older. The cohort had a mean age of 72 and was predominantly female (63%) and white (81%).
Serial TMAO levels were measured using liquid chromatography paired with tandem mass spectrometry. Baseline abdominal ultrasonography was completed in 3,961 participants. Participants were deemed to have an AAA if their infrarenal aortic diameter was ≥ 3.0 cm or an infrarenal-to-suprarenal aortic width ratio ≥ 1.2.
Advertisement
Prospective surveillance tracked the composite of clinical AAA events, which were defined as surgical intervention, aneurysm rupture or AAA-induced death. Participants were followed for a median of 12.2 years, resulting in 54,402 person-years of follow-up.
The study yielded notable findings in several areas.
At the initial ultrasound screening, 335 participants (8.5%) were diagnosed with an AAA. Baseline TMAO levels were significantly higher in individuals with an AAA than in those without. In fact, each doubling of baseline TMAO level was associated with an approximately 0.3-cm increase in infrarenal aortic diameter. After adjustment for a wide range of demographic and health variables, participants in the highest quintile of TMAO levels had a 73% higher odds of having an ultrasound-detected AAA compared with those in the lowest quintile (odds ratio = 1.73; 95% CI, 1.17-2.58).
Over the follow-up period, 79 participants experienced at least one adverse AAA event, consisting of 53 operative repairs, 25 ruptures and 15 deaths related to the aneurysm. Higher serial TMAO levels were strongly linked to a higher likelihood of clinical AAA events.
In multivariable-adjusted Cox regression survival models controlling for typical cardiovascular covariates, participants in the highest tertile of TMAO values (6.40 to 255 µM) had a 2.46-fold increased risk of adverse aortic events relative to those in the lowest tertile (< 3.72 µM). This association remained significant even after further adjustment for renal function (adjusted hazard ratio = 2.09; 95% CI, 1.09-4.01), which is a key determinant of TMAO clearance, and other lifestyle, socioeconomic and dietary variables.
Advertisement
When analyzed as a continuous variable, each doubling of TMAO concentration increased the hazard of an adverse AAA event by 28%. Using a clinically established TMAO threshold of ≥ 6.2 µM (corresponding to the 75th percentile in cardiovascular risk cohorts), the researchers found that participants above this cutoff had a 93% higher hazard of experiencing an adverse AAA event.
Adding TMAO to standard clinical risk models significantly improved predictive discrimination across yearly horizons, the investigators found. Two different statistical methods demonstrated that TMAO measurement significantly improved the accuracy of identifying high-risk patients.
“Surgeons have traditionally relied heavily on aneurysm diameter and growth to determine when intervention is warranted, but these findings suggest that the biology of the aneurysm may be equally important,” says Francis Caputo, MD, Vascular Surgery Director of Cleveland Clinic’s Aorta Center, who wasn’t involved in the study. “TMAO has the potential to give us a window into that biology and, if these findings are confirmed in prospective studies, could fundamentally change how we risk-stratify and ultimately treat patients with AAA.”
These findings have immediate and long-term implications, the investigators note. First, measuring TMAO levels in the blood can help refine risk assessment, particularly for patients with small, borderline or stable aneurysms undergoing imaging surveillance.
Second, because the gut microbial pathway is highly modifiable, it presents a unique therapeutic opportunity. Unlike genetic risk factors, TMAO can be actively reduced using several clinical strategies:
Advertisement
The investigators note some limitations to their study, including a lack of AAA family history data and limited racial heterogeneity. Nevertheless, the findings were remarkably consistent across clinical and demographic subgroups. While the association was stronger in men, it remained directionally consistent in women, whose AAAs typically expand less predictably and tend to rupture at smaller diameters.
“These findings provide a solid scientific rationale for initiating clinical intervention trials in humans,” says Dr. Hazen, noting that further research should evaluate whether aggressively lowering TMAO levels through diet or targeted microbial therapeutics can slow AAA expansion and prevent catastrophic ruptures. “Until such trials are conducted, measuring TMAO levels in patients with borderline aortic dilation may offer a valuable tool for risk stratification and a powerful motivator for lifestyle modification.”
“This is as close as this field has come to identifying a nonsurgical therapeutic agent for a high-quality clinical trial — one that Cleveland Clinic is well positioned to lead,” Dr. Cameron concludes.
Advertisement
Large analysis adds to evidence that absolute diameter alone may miss vulnerable patients
Height-indexed aortic measurements may better identify risk than diameter alone
‘Sac flow’ is more precise and will ease unfounded patient concerns, experts argue
Robust signal from observational study raises prospect of a long-sought medical therapy
Expert advice on repair vs. replacement, timing of surgery in asymptomatic cases and much more

Series of 145 patients characterizes scope of presentations, interventions and outcomes
New Cleveland Clinic data challenge traditional size thresholds for surgical intervention
Study finds comparable midterm safety outcomes, suggesting anatomy and surgeon preference should drive choice
 Search