Locations:


Milestone case report expands understanding of infectious risks for those on immunomodulatory therapies
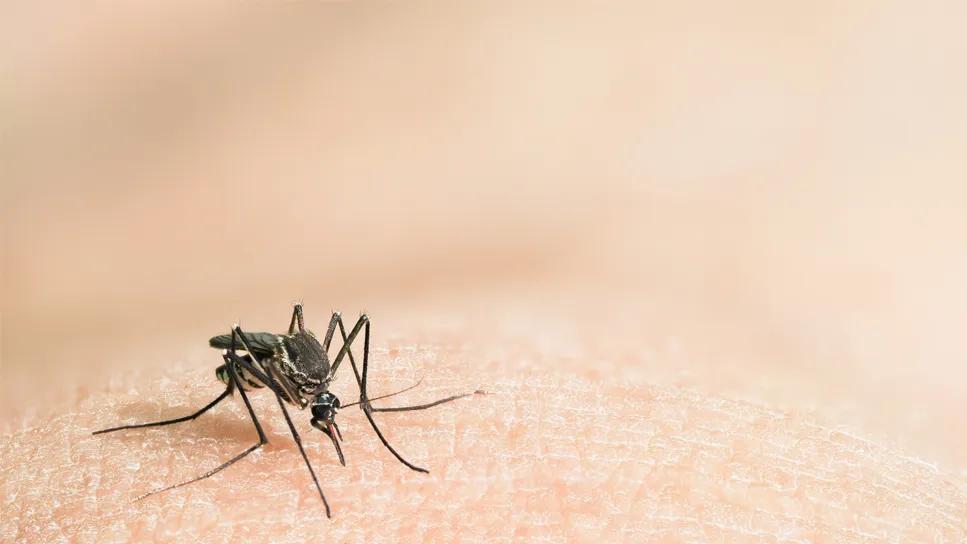
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/21fafea3-7cab-44fb-8446-3cb4c5578c29/mosquito-on-arm-2246936919)
mosquito on human skin
The mosquito-borne Potosi virus is a neuroinvasive human pathogen, according to a new case report from Cleveland Clinic clinicians and researchers published in Neurology.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
The report is the first to confirm, through postmortem neuropathological analysis and collaboration with the U.S. Centers for Disease Control and Prevention (CDC), that Potosi virus is a human pathogen causing severe central nervous system (CNS) infection. The one previous report also came from a Cleveland Clinic infectious disease specialist, but definitive tissue confirmation was not available in that case.
The new report details a fatal case of Potosi virus meningoencephalitis in a 37-year-old woman with multiple sclerosis (MS) receiving long-term B cell-depleting therapy with rituximab.
“This case shows that even younger, relatively healthy patients on B-cell depleting therapies like rituximab can develop severe, atypical infections without traditional risk factors such as older age or multiple comorbidities,” says the report’s first and corresponding author, Justin Abbatemarco, MD, a neurologist with Cleveland Clinic’s Center for Multiple Sclerosis Treatment and Research who helped lead management of the case.
“Rituximab and other CD20 monoclonal antibody therapies that deplete harmful B cells are extremely useful for treating MS and many other autoimmune diseases,” he continues. “So this finding shouldn’t deter us from their use, but it should prompt us to counsel patients a bit differently, to make clear that rare infections can develop even without the risk factors we would usually discuss when initiating these therapies.”
The patient was a 37-year-old woman with long-standing MS that was well controlled with rituximab (1,000 mg every six months), which had been initiated in November 2020. Her last infusion was in November 2024, at which time she had undetectable CD19+ cell counts and normal immunoglobulin G levels.
Advertisement
She developed neuropsychiatric deficits in mid-2024. Her risk profile was notable only for frequent time spent outdoors with mosquito exposure in her Ohio community.
By January 2025 she was experiencing worsening mood symptoms, executive function and short-term memory as well as vertigo, incoordination and gait instability. She became unable to care for herself or others. At examination in April 2025 she was oriented but lethargic and had appendicular and truncal cerebellar ataxia and global hyperreflexia without meningismus.
Longitudinal MRI showed chronic findings consistent with MS, but from January 2024 to January 2025 these were accompanied by marked progressive generalized brain atrophy without inflammatory features suggestive of encephalitis. “The severe atrophy was out of proportion to anything we would see in MS over the course of a few months,” Dr. Abbatemarco observes.
CSF analysis was notable only for minimal and transient lymphocytic pleocytosis. Conventional infectious, autoimmune and prion testing was otherwise unrevealing apart from hypogammaglobulinemia.
By May 2025 she was experiencing visual hallucinations, hyperactive movements and catatonic posturing. Agnostic metagenomic sequencing of the CSF demonstrated high-confidence RNA reads that aligned to all three segments of the Potosi virus genome.
The patient was comatose at the time of metagenomic testing and died two weeks after being moved to comfort care.
The family consented to postmortem brain examination, which showed meningoencephalitis with T cell-predominant leptomeningeal inflammation and perivascular lymphocytic inflammation with diffuse microgliosis occasionally forming microglial nodules. There was widespread neuronal loss and dystrophic neurons in the cerebral cortex with evidence of neuronophagia.
Advertisement
Infection was then confirmed by postmortem molecular and tissue-based studies done in conjunction with the CDC:
Potosi virus is a mosquito-borne orthobunyavirus in the family Peribunyaviridae. It had previously been isolated from mosquitoes in the U.S., and there had been at least one prior human case suggestive of CNS disease, but direct proof of brain infection was lacking
The case report authors note that their findings were concordant across multiple laboratories at Cleveland Clinic and the CDC, definitively establishing Potosi virus as a human pathogen for fatal neuroinvasive disease.
They further conclude that chronic B cell depletion with CD20 monoclonal antibodies may predispose patients to rare severe CNS infections with atypical presentations that include progressive cognitive and psychiatric decline, generalized cerebral atrophy, and little or no conventional CSF or MRI evidence of inflammation.
Advertisement
This elevates the importance of counseling patients with MS and other conditions treated by B cell-depleting therapies about infection risks, including mosquito avoidance and use of insect repellents, particularly as climate change increases the prevalence of vector-borne diseases. “I’ve started incorporating this into my discussions with patients on these therapies,” Dr. Abbatemarco notes.
The case also argues for greater clinical vigilance for atypical presentations of neuroinvasive infections in these patients — even in the absence of traditional risk factors like advanced age, multiple comorbidities and long-term use of immunomodulatory therapy — and underscores the limits of standard diagnostics in this setting.
“A key takeaway is that CSF metagenomic sequencing can be very helpful in scenarios like this where standard testing is unrevealing,” Dr. Abbatemarco says. He notes that metagenomic sequencing is expensive, however, and requires infectious disease consultation, which underscores the need for referral of challenging cases to tertiary centers.
Indeed, he emphasizes that successful diagnosis and confirmation of the rare infection in this case were made possible by a degree of multidisciplinary collaboration within and beyond Cleveland Clinic unprecedented in his career. The effort involved outpatient and inpatient neurologists, infectious disease specialists, neuropathologists, and scientists in three different Cleveland Clinic labs — and ultimately in labs at the CDC.
Advertisement
“Our integrated care model made it possible to go from bedside to bench to get the answers we needed and also to better understand this threat for the sake of future patients,” Dr. Abbatemarco observes. “That collaboration between the clinic and the lab was special.”
Continuation of such collaboration will be key to future research into Potosi virus as a neuroinvasive human pathogen. Research priorities include understanding mechanisms of how the virus enters and spreads in the brain and determining its prevalence, according to Dr. Abbatemarco. “We are now partnering with our CDC colleagues to help answer some of these questions,” he concludes.
Advertisement

Advanced technologies are changing expectations about what’s possible
Multidisciplinary, proactive approach also improved discharge outcomes

Designed for digitization, distance health, discovery and more

Combining customized care, research capabilities and flexibility for the future
Expanded bevy of dedicated ORs will feature customized designs, leading-edge technology, optimized workflows

Routine capture of standardized neuroperformance data may expand and refine investigations

Reimagining the outpatient neurological visit with routine capture of neuroperformance data

Advanced surgical suite in our soon-to-open facility promises to redefine care standards
 Search