Locations:


Change eliminates waste associated with dual-field approach
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/07876897-d7c7-4298-aa9b-ec010144dfbc/surgical-draping-cqd)
Close-up images of IVs
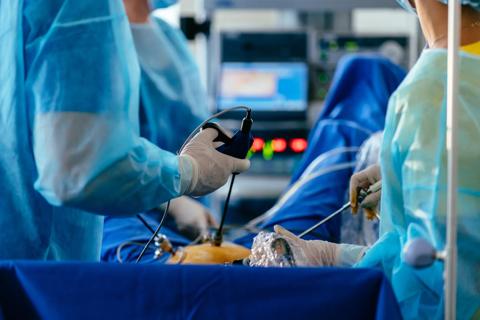
Cleveland Clinic surgeons performing laparoscopic or robotic techniques for gynecological procedures developed a new protocol to treat the abdominal and perineovaginal areas as a unified single surgical field.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
Out of concern for cross contamination, the preparation, draping and maintenance of a sterile field for each site has traditionally been treated separately. But Cleveland Clinic surgeon Cara King, DO, MS, says emerging data suggest that sterility can be maintained when a unified single-field approach is used.
“For a long time, the assumption in the OR has been that the abdominal field is clean and the vaginal or perineal field is contaminated, and that has led to repeated glove changes and a lot of workflow disruption. In some settings, if you had worked in the vaginal field and then touched the light handle, that handle had to be changed too,” says Dr. King, Section Head of Minimally Invasive Gynecologic Surgery and Medical Gynecology. “Whether this approach has served us well has been a common conversation across institutions, because many of us have seen that infection rates do not rise when those transitions are handled under a unified sterile field approach.”
The new guideline, introduced in early 2026, was developed to improve surgical efficiency, reduce cost and waste, and maintain patient safety and quality outcomes. At Cleveland Clinic, the key steps begin with administering antibiotic prophylaxis and following the health system’s universal safety checklist.
During field preparation, an alcohol-based (2% CHG/70% alcohol) antiseptic is used for the abdomen and 4% chlorhexidine vaginal prep or Providine iodine is used for the perineovaginal area. Although the two areas require different preparatory solutions and separate applicators, the operative field is considered unified. The surgeons follow the health system’s standard operating procedures for prep solution application.
Advertisement
The new protocol allows surgeons to use their discretion when applying drapes to separate the abdominal and perineal fields or to maintain a continuous sterile field. While the guideline stipulates that separate instrument tables or trays may be used for abdominal and vaginal instruments, they are not be considered separate sterile fields.
Under the single unified sterile field approach:
Minimally invasive or robotic procedures for which the new guidelines might be used include:
Advertisement
“This work is really about continuous improvement,” says Dr. King. “We should always be willing to reexamine long-standing protocols when the evidence and our clinical experience show there may be a better way. If we can maintain or improve patient outcomes while also reducing unnecessary steps, saving time and using resources more responsibly, that is meaningful progress.”
Advertisement
Advertisement
Researchers compare two image modes in detecting left ventricular remodeling

Nutrition and cooking program supports maternal-infant health
New moniker brings clarity to this complex condition

A device implanted at the ankle joins the lineup of third-line treatments
Aiming for earlier detection of endometrial cancer in an era of increasing incidence
Minimally invasive surgery is the preferred approach in many cases, but not all
Patients deserve timely diagnosis and a multidisciplinary approach

Data point to potential for targeted preconception planning
 Search